
 By Gilang Cahya
Millions of Americans undergo annual blood tests to assess their low-density lipoprotein (LDL) cholesterol, commonly referred to as "bad" cholesterol. However, groundbreaking new research emerging from Northwestern Medicine indicates that an alternative blood marker, apolipoprotein B (apoB), may provide a more precise and effective means of identifying individuals who would benefit from more aggressive treatment strategies to mitigate the risks of heart attacks and strokes. This pivotal study, published in the prestigious JAMA, suggests a significant shift in how cardiovascular risk is assessed and managed within the U.S. healthcare system.
The research team found that measuring apoB was demonstrably more effective than traditional LDL or non-high-density lipoprotein (non-HDL) cholesterol levels when determining the necessity of intensifying cholesterol-lowering therapies, a category that includes widely prescribed statins and other advanced medications. This finding carries profound implications for preventative cardiology, potentially leading to improved patient outcomes and more efficient allocation of healthcare resources.
"We found that apoB testing to intensify cholesterol-lowering medication would prevent more heart attacks and strokes than current practice, and that these health benefits were achieved at a cost that represents good value for U.S. healthcare payers," stated Ciaran Kohli-Lynch, the study’s lead author and an assistant professor of preventive medicine in the division of epidemiology at Northwestern University Feinberg School of Medicine. This assertion is particularly noteworthy as it is the first comprehensive analysis to systematically demonstrate that utilizing apoB to guide cholesterol treatment is not only clinically superior but also economically sound.
The Enduring Burden of Heart Disease and the Need for Enhanced Risk Assessment
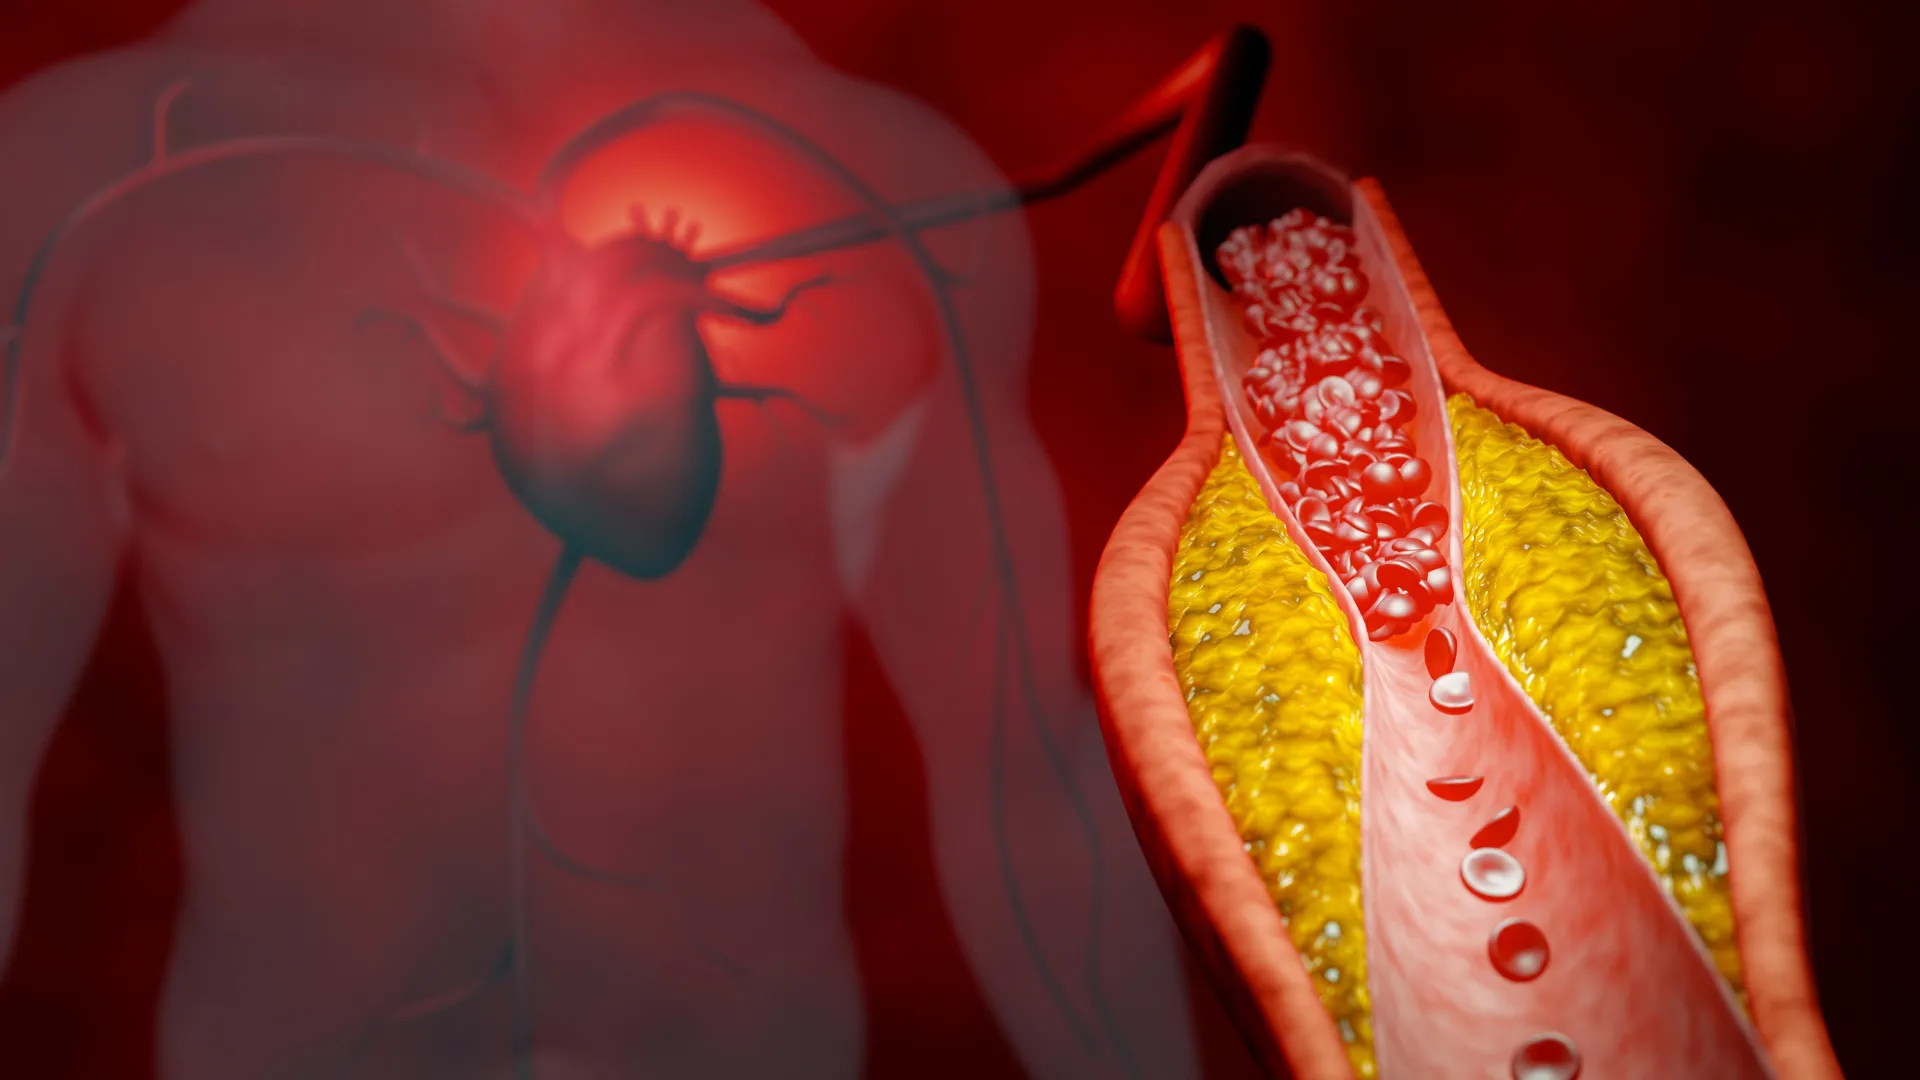
Heart disease continues to hold its position as the leading cause of mortality in the United States, contributing to a substantial portion of the nation’s healthcare expenditures. The underlying mechanism of this disease involves the gradual accumulation of cholesterol-laden particles within the arterial walls. Over time, these particles can transform into plaques, narrowing the arteries, impeding blood flow, and significantly elevating the risk of life-threatening cardiovascular events such as heart attacks and strokes.
For decades, clinicians have relied on LDL and non-HDL cholesterol measurements as primary indicators for initiating or intensifying cholesterol-lowering interventions. While these tests have provided valuable insights, their ability to fully encapsulate an individual’s complex cardiovascular risk profile has been increasingly questioned. This is where the significance of apoB measurement comes into sharper focus.
Apolipoprotein B: A More Direct Indicator of Cardiovascular Risk
"Research strongly shows that apolipoprotein B (apoB) is better at identifying who is at risk, because it counts the total number of harmful particles in the blood," explained Kohli-Lynch. Unlike conventional cholesterol tests that measure the amount of cholesterol within particles, apoB quantifies the actual number of apolipoprotein B-containing particles. These are precisely the particles that are atherogenic, meaning they are capable of contributing to the formation of arterial plaques.
The crucial distinction lies in the fact that apoB directly measures the number of cholesterol-carrying particles that can lodge in and damage artery walls, thereby serving as a more direct and potent indicator of cardiovascular risk. Even with a growing body of evidence supporting its utility, apoB testing has not yet become a routine component of standard cardiovascular care. A primary barrier has been the perceived increased cost and inconvenience, as measuring apoB often requires an additional blood draw beyond the typical lipid panel.
"Our study asked: Is it worth spending extra money to use apoB instead of LDL to guide treatment intensification?" Kohli-Lynch elaborated, highlighting the core question the research sought to answer. The study aimed to provide a definitive, evidence-based answer to this crucial economic and clinical dilemma.
A Sophisticated Simulation Unveils the Superiority of ApoB Testing
To rigorously address this question, the Northwestern Medicine research team employed a sophisticated computer simulation model. This model was designed to represent a cohort of 250,000 U.S. adults who were deemed eligible for statin therapy but had not yet developed pre-existing cardiovascular disease. This demographic represents a critical population for primary prevention strategies.
The simulation meticulously compared three distinct approaches to guiding lipid-lowering treatment intensification:
- Strategy 1: LDL Cholesterol Goals: This approach adhered to the current standard of care, where treatment intensification is guided by whether a patient’s LDL cholesterol levels meet established targets.
- Strategy 2: Non-HDL Cholesterol Goals: This strategy employed non-HDL cholesterol levels as the primary metric for treatment decisions. Non-HDL cholesterol is calculated by subtracting HDL cholesterol from total cholesterol and is considered a broader measure of atherogenic lipoproteins.
- Strategy 3: Apolipoprotein B (apoB) Goals: This innovative strategy utilized apoB levels as the decisive factor for intensifying treatment.
Within each simulated strategy, when patients failed to achieve their designated lipid-lowering targets, the treatment regimen was escalated. This escalation typically began with the prescription of more potent statin medications, followed by the addition of other lipid-lowering drugs such as ezetimibe if further reduction was deemed necessary.
The research team tracked the simulated patients over their lifetimes, meticulously estimating key health outcomes. These estimations included the incidence of heart attacks and strokes, overall life expectancy, quality-adjusted life years (a measure that accounts for both the length and quality of life), and the cumulative healthcare costs associated with each strategy.
The results of this comprehensive simulation were compelling and consistent. The strategy that employed apoB levels to guide treatment consistently outperformed both the LDL and non-HDL cholesterol-based approaches. It not only led to improved overall health outcomes and a greater prevention of cardiovascular events but did so in a manner that the researchers unequivocally determined to be cost-effective. This suggests that the initial investment in more precise risk assessment through apoB testing can lead to significant long-term savings by preventing more costly cardiovascular events.
Evolving Guidelines Underscore the Imperative for Accurate Risk Stratification
These findings arrive at a particularly opportune moment, coinciding with a dynamic period in cardiovascular medicine. The therapeutic landscape has expanded significantly, with a greater array of cholesterol-lowering medications available to clinicians than ever before. Furthermore, earlier this year, the American Heart Association, in conjunction with ten other leading medical organizations, released updated clinical guidelines. These revised guidelines advocate for the initiation of cholesterol-lowering therapy at younger ages for a broader segment of the population.
"This means it is increasingly important to accurately identify who would benefit most from intensive treatment," emphasized Kohli-Lynch. The increased emphasis on early intervention and the availability of diverse treatment options necessitate a more refined understanding of individual risk to ensure that the right patients receive the right therapies at the right time. The Northwestern Medicine study provides robust evidence that apoB measurement is a critical tool for achieving this precision.
The implications of this research extend beyond individual patient care. For U.S. healthcare payers, including insurance providers and government programs, the findings suggest a pathway to optimize resource allocation. By identifying high-risk individuals more accurately through apoB testing, healthcare systems can proactively invest in more aggressive preventative measures, potentially averting the substantial financial burden associated with treating advanced cardiovascular disease.
Broader Impact and Future Directions
The study’s authors, including Drs. John Wilkins and Samuel Luebbe from Northwestern, have provided a foundational piece of research that could reshape clinical practice. The study, titled "Cost-Effectiveness of ApoB, Non-HDL-C, and LDL-C Goals for Primary Prevention Lipid-Lowering Therapy," was supported by the American Heart Association Career Development Award, underscoring the significance and recognition of this work within the cardiology community.
While the current study focused on primary prevention in individuals without established cardiovascular disease, the findings logically extend to secondary prevention, where patients have already experienced a cardiovascular event. In such cases, the stakes are even higher, and precise risk assessment is paramount to prevent recurrence. Future research could explore the cost-effectiveness and clinical utility of apoB testing in these higher-risk populations.
The widespread adoption of apoB testing would necessitate an adjustment in laboratory protocols and physician education. However, the potential to prevent a significant number of heart attacks and strokes, coupled with the demonstration of cost-effectiveness, provides a powerful argument for its integration into routine cardiovascular risk assessment. As the field of preventative cardiology continues to evolve, embracing more accurate and informative diagnostic tools like apoB measurement will be crucial in the ongoing fight against heart disease, the leading cause of death globally. The Northwestern Medicine study offers a compelling roadmap for achieving this vital objective.
