
 By Budi Oetomo Narendra
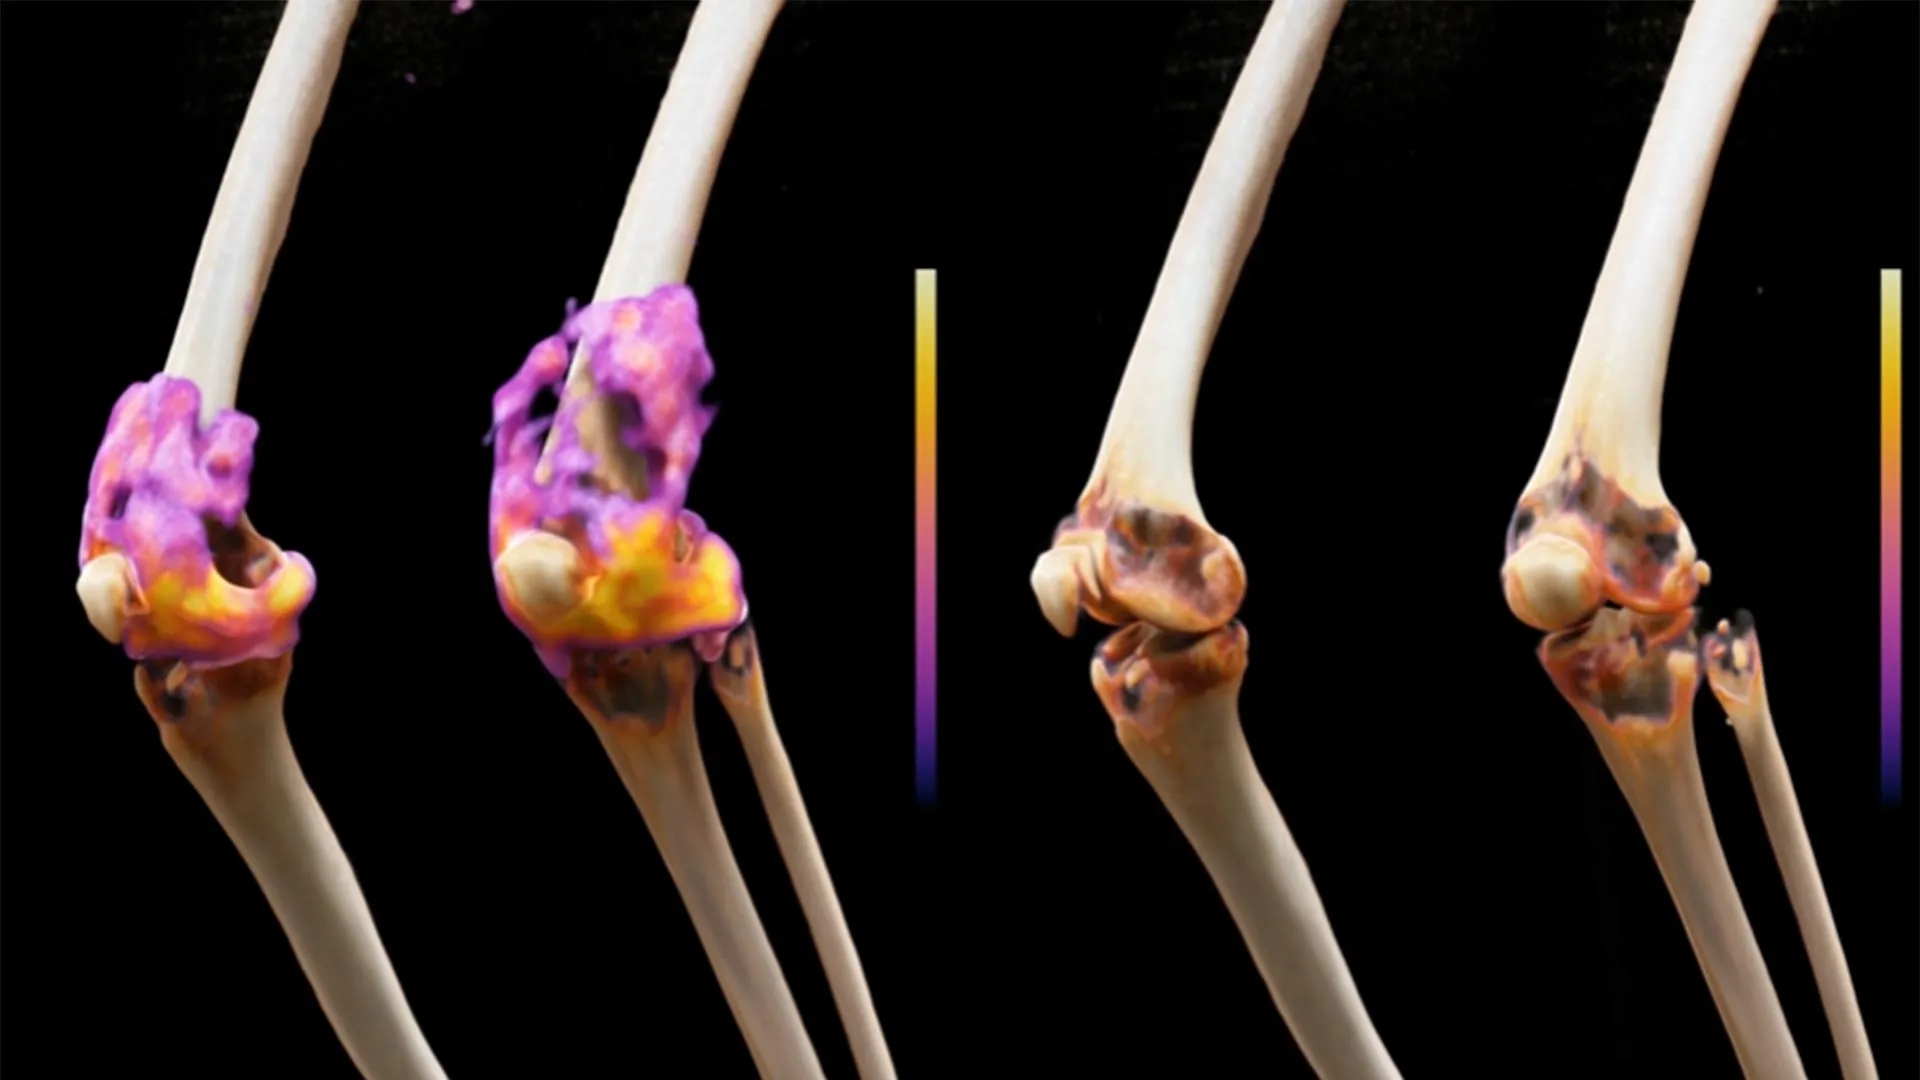
The landscape of medical treatment is continually evolving, and a groundbreaking development originating from the realm of cancer therapy is now offering a beacon of hope for patients battling severe autoimmune diseases. Immunotherapies, notably CAR T-cell therapy, were initially conceived and refined primarily to combat various forms of cancer, harnessing the body’s own immune system to target malignant cells. However, a transformative shift is underway as scientists worldwide investigate the potential of these highly personalized treatments, meticulously engineered from a patient’s own immune cells, to not only manage but potentially cure debilitating autoimmune conditions. A recent clinical trial conducted at Charité – Universitätsmedizin Berlin has brought this promise closer to reality, yielding encouraging early results in the application of CAR T-cell therapy for individuals suffering from particularly severe, treatment-refractory rheumatoid arthritis.
The Genesis of CAR T-Cell Therapy: From Oncology to Immunology
Chimeric Antigen Receptor (CAR) T-cell therapy represents a cutting-edge form of immunotherapy that has revolutionized the treatment of certain blood cancers, particularly leukemias and lymphomas. Its genesis lies in the sophisticated manipulation of a patient’s own T-cells – a type of white blood cell crucial to the immune system’s adaptive response. In the context of oncology, these T-cells are extracted from the patient, genetically modified in a laboratory to express a CAR. This artificial receptor is designed to recognize and bind to specific proteins (antigens) found on the surface of cancer cells. Once infused back into the patient, these ‘supercharged’ CAR T-cells proliferate, seeking out and destroying tumor cells with remarkable precision and efficacy. Approved by regulatory bodies like the U.S. Food and Drug Administration (FDA) and the European Medicines Agency (EMA) for conditions such as refractory B-cell acute lymphoblastic leukemia and large B-cell lymphoma, CAR T-cell therapy has demonstrated its formidable power in eliminating persistent cancer cells that have resisted conventional treatments.
The underlying principle of CAR T-cell therapy – the highly targeted elimination of specific cell populations – naturally led researchers to consider its applicability beyond cancer. Autoimmune diseases, characterized by an immune system mistakenly attacking healthy tissues and organs, often involve specific immune cell subsets that drive the pathological process. The idea emerged: if CAR T-cells could be directed against these disease-driving immune cells, much like they target cancer cells, could they halt or even reverse autoimmune pathology? This conceptual leap has opened an entirely new frontier in immunology and therapeutic development, with rheumatoid arthritis becoming one of the first major targets for this innovative approach.
The Autoimmune Challenge: Understanding Rheumatoid Arthritis and its Unmet Needs
Rheumatoid arthritis (RA) stands as a prominent and debilitating chronic autoimmune disease, affecting approximately 0.5% to 1% of the global adult population, translating to tens of millions worldwide. Women are disproportionately impacted, with a prevalence two to three times higher than in men. In RA, the immune system erroneously identifies the synovial lining of joints as a threat, initiating a relentless inflammatory assault. This sustained inflammation leads to excruciating pain, swelling, stiffness, and over time, irreversible damage to cartilage and bone, culminating in joint deformity and significant functional impairment. Beyond the joints, RA can manifest systemically, affecting vital organs such as the heart, lungs, and eyes, and significantly increasing the risk of cardiovascular disease, a leading cause of mortality in RA patients.
Current therapeutic strategies for RA primarily focus on controlling inflammation and suppressing the immune system to mitigate disease progression. These include conventional synthetic disease-modifying antirheumatic drugs (csDMARDs) like methotrexate, and more recently, targeted biologic and synthetic DMARDs (bDMARDs and tsDMARDs), which specifically block inflammatory pathways or target certain immune cells. While these medications have dramatically improved outcomes for many patients, preventing severe joint destruction and improving quality of life, they rarely offer a cure. The majority of individuals with RA require lifelong treatment, which can be associated with side effects ranging from increased susceptibility to infections to liver toxicity and other systemic complications.
A significant challenge remains for a subset of patients whose disease proves "treatment-refractory." These individuals experience persistent pain, limited mobility, and a profound reduction in their quality of life despite exhausting multiple lines of conventional and advanced therapies. For them, the existing medical arsenal falls short, leaving them with chronic suffering and an urgent need for novel, more effective interventions. The conventional approach of continuous immune suppression, while often necessary, does not address the root cause – the underlying pathological immune memory that perpetually "reignites" the inflammation. It is precisely this unmet need that the pioneering research at Charité aims to address by offering a potential "immune reset."
The Charité Trial: A Landmark Study for Severe RA
Researchers at Charité – Universitätsmedizin Berlin embarked on the world’s first clinical trial of its kind, meticulously designed to evaluate the safety and efficacy of CD19 CAR T-cell therapy in individuals with severe, treatment-refractory rheumatoid arthritis. This landmark study, reported in the prestigious journal Nature Medicine, represents a significant milestone in the quest to harness advanced immunotherapies for autoimmune conditions.
Professor David Simon, who spearheaded the trial’s design for this specific patient cohort alongside Professor Gerhard Krönke at Charité’s Department of Rheumatology and Clinical Immunology, articulated the core hypothesis guiding their innovative approach: "One reason could be disease-driving B cells – memory cells of the adaptive immune system that may survive in the lymph nodes, bone marrow or joint tissue after an infection, where they produce harmful antibodies directed against the body’s own tissues and repeatedly reignite the inflammation." The objective was to determine if CAR T cells could precisely seek out and eliminate these deeply entrenched, disease-driving B cells, thereby clearing the "abnormal B-cell memory" and effectively orchestrating a profound "reset" of the B-cell system. This targeted approach contrasts sharply with broader immunosuppressive therapies that can affect the entire immune system.
Mechanism of Action: Reprogramming the Immune System to Fight Autoimmunity
The adaptation of CAR T-cell therapy from cancer to autoimmune diseases hinges on a critical shared target: the CD19 surface molecule. As Professor Simon elucidated, "The identifying marker on many B cells, both abnormal B cells in cancers of the blood or lymphatic system and disease-driving B cells in rheumatoid arthritis, is the surface molecule CD19. You could think of it as a kind of ‘name tag’." This ubiquitous marker on B cells makes it an ideal target for a therapeutic intervention aimed at broadly depleting this cell population, which is central to the pathogenesis of many autoimmune diseases.
The process of CD19 CAR T-cell therapy for RA mirrors that used in cancer treatment, involving several intricate steps executed with precision and specialized infrastructure:
- T-cell Collection (Apheresis): T cells, vital components of the patient’s immune system, are first collected from their blood through a specialized procedure called apheresis. This outpatient procedure typically takes several hours and involves separating T cells from other blood components.
- Genetic Modification: In a highly controlled, specialized laboratory setting (often referred to as a "clean room" or Good Manufacturing Practice, GMP facility), these isolated T cells are genetically engineered. A viral vector, often a lentivirus or retrovirus, is typically used to introduce a gene that codes for the chimeric antigen receptor (CAR). This CAR is specifically designed to recognize and bind to the CD19 protein found on the surface of B cells.
- Cell Expansion: The newly modified CAR T cells are then cultured and expanded in large numbers over several weeks, creating a potent therapeutic dose sufficient for infusion. This critical step ensures enough engineered cells are available to exert a therapeutic effect.
- Preparatory Chemotherapy: Before receiving the engineered cells, patients undergo a brief course of lymphodepleting chemotherapy. This crucial step temporarily reduces the number of existing immune cells, creating an optimal environment for the CAR T cells to engraft, multiply, and function effectively without being outcompeted by the patient’s endogenous immune cells. This "space-making" chemotherapy typically involves agents like fludarabine and cyclophosphamide.
- Infusion: The expanded and quality-controlled CAR T cells are then re-infused back into the patient, typically as a single intravenous infusion. This is a critical moment, as the living drug begins its work.
Once inside the body, these re-engineered T cells become a highly targeted search-and-destroy force. They actively seek out and bind to any cell expressing the CD19 marker, including the long-lived, pathogenic B cells that reside in difficult-to-reach "reservoirs" such as the bone marrow, lymph nodes, and inflamed joint tissues. By systematically eliminating these CD19-positive B cells, the treatment aims to clear the immunological slate, allowing for a fresh start for the immune system and potentially breaking the cycle of chronic inflammation.
The COMPARE Trial: Participant Profile and Early, Encouraging Results
For the initial phase of the COMPARE trial, the Charité team meticulously selected six patients who represented the most challenging cases of rheumatoid arthritis. The cohort comprised three women and three men, aged between 31 and 69 years, all grappling with particularly severe, treatment-refractory disease. A telling detail of their medical history was the extensive number of prior treatments they had undergone: over the preceding decade, these individuals had received as many as eight different targeted or biologic therapies, yet none had managed to adequately control their disease activity. Their persistent symptoms underscored the urgent need for a truly novel therapeutic approach, as their quality of life was severely compromised.
The primary objectives of this first-in-human phase were dual: to assess the safety profile of CD19 CAR T-cell therapy in RA patients and to gain preliminary insights into its clinical effectiveness. The results, as reported by the research team, were profoundly encouraging and exceeded expectations for such a challenging patient population.
"Disease activity decreased markedly in all six patients. During follow-up of up to one year, three patients were in sustained remission without any medication for rheumatoid arthritis," stated Professor Gerhard Krönke, who co-leads the joint Clinical Rheumatology research group at Charité and the German Rheumatology Research Center (DRFZ), a Leibniz Institute. He emphasized the significance: "This is particularly remarkable given that none of the established treatments had previously been able to relieve their symptoms adequately." This outcome – half of the severely affected patients achieving sustained, medication-free remission – represents an unprecedented level of response for this challenging patient population, offering a glimpse into the potential for a true disease-modifying intervention.
Unpacking the "Immune Reset": Reaching Hidden Reservoirs and Reprogramming Memory
The profound clinical improvements observed were not merely a temporary reduction in inflammation. The researchers delved deeper to understand the immunological mechanisms at play, seeking evidence of a fundamental shift in the immune system. A key finding was the ability of the modified immune cells to reach and eliminate disease-promoting B cells not only in the bloodstream but also in deeper, more protected locations, including the bone marrow, lymph nodes, and crucially, the inflamed joint tissue itself. These anatomical sites are known to harbor long-lived memory B cells that can perpetuate autoimmune responses, making their elimination a critical step towards sustained remission. Traditional B-cell depleting therapies often struggle to reach these deeply embedded reservoirs effectively.
Following the CAR T-cell infusion, regular follow-up visits over the subsequent 12 months revealed a dramatic reduction in the levels of autoantibodies – the self-reactive antibodies characteristic of rheumatoid arthritis – in the patients’ blood. This decline served as a tangible biomarker reflecting the profound depletion of the autoantibody-producing B cell population, directly correlating with clinical improvement.
Professor David Simon elaborated on an even more significant immunological observation that points to a potential "immune reset": "When the B-cell system later recovered, predominantly naïve B cells that had not yet been shaped by the disease returned. In contrast, the B cells directed against the body’s own tissues that had been present before treatment were no longer detectable in almost all patients, an indication that the treatment may indeed be able to reset the pathological immune memory." This suggests that the CAR T-cell therapy not only clears out the ‘bad’ B cells but allows for a repopulation of the B-cell compartment with new, untainted cells, potentially erasing the autoimmune memory that drives the disease. This concept of an "immune reset" is a holy grail in autoimmune disease research, offering the hope of long-term disease control or even cure, rather than just symptom management.
Importantly, the researchers also addressed a critical safety concern: the potential for broad B-cell depletion to compromise protective immunity against common pathogens. Their findings showed that antibodies generated by earlier vaccinations, such as those against chickenpox and tetanus, could still be detected in the patients. This suggests that while the therapy caused a profound temporary depletion of B cells, the long-term, protective antibody memory – which is crucial for defending against common pathogens – was largely preserved. This distinction is vital for the long-term safety profile of such a therapy, though further investigation into the therapy’s longer-term effects on the overall immune system, including responses to new infections or vaccinations, is still necessary.
Expert Perspectives and Scientific Rationale
The consensus among the research team points to the unique ability of CAR T-cells to offer a "hard reset" to the immune system, a feat beyond the capabilities of current therapies. Professor Krönke highlighted the unprecedented nature of achieving medication-free remission in such difficult-to-treat patients, underscoring the potential for a paradigm shift in how chronic autoimmune diseases are approached. Dr. Marie Luise Hütter-Krönke, Medical Director of the Hematology Early Clinical Trial Unit at Charité’s Department of Hematology, Oncology and Cancer Immunology, provided crucial insights into the observed safety profile. "After the participants received the CD19 CAR T cells, we observed only a temporary, mild-to-moderate cytokine release syndrome (CRS) in all participants, which was readily manageable. There were no severe neurological complications or other serious adverse events, and infections were rare," she explained. This safety data, particularly the absence of severe neurological complications (known as ICANS or immune effector cell-associated neurotoxicity syndrome), which have been a concern in some cancer CAR T-cell trials, is highly encouraging for the application in autoimmune settings where patients are generally less debilitated than cancer patients.
The scientific rationale for targeting CD19-positive B cells in autoimmune diseases is robust. B cells play multiple, interconnected roles in autoimmunity: they produce pathogenic autoantibodies, present autoantigens to T cells, and secrete pro-inflammatory cytokines that perpetuate the inflammatory cascade. By eliminating this critical cell population, CAR T-cell therapy effectively disrupts several key pathogenic pathways simultaneously. The challenge has always been to achieve a deep and sustained depletion without unacceptable toxicity, and the Charité trial offers promising evidence that this delicate balance might be achievable.
Safety Profile and Current Limitations: A Realistic Outlook
While the initial safety findings are encouraging, it is imperative to acknowledge that CAR T-cell therapy for autoimmune diseases remains experimental. The observed side effects, primarily a temporary, mild-to-moderate cytokine release syndrome (CRS), are a known and anticipated complication of CAR T-cell therapy and are generally manageable with supportive care, including
