
 By admin
The Cancer Research Institute (CRI) has announced a groundbreaking shift in its funding strategy, dedicating its prestigious CLIP (Cancer-focused Long-term Interception Program) applications for the first time to a singular, critical scientific theme: primary and secondary cancer prevention and interception. This strategic pivot signals a deepening commitment to stopping cancer before it takes root or returns, aiming to fundamentally reshape the future of oncology. The institute is actively seeking multi-investigator teams whose research seamlessly bridges fundamental mechanistic discovery with practical clinical application, with the ultimate goal of advancing innovative immune-based strategies to prevent or intercept the development and recurrence of cancer. This initiative represents a profound recognition that the battle against cancer must increasingly be fought in the pre-diagnostic phase, leveraging the immune system’s inherent capabilities.
A Paradigm Shift: From Treatment to Pre-emption
For generations, the narrative of cancer care has largely revolved around diagnosis and treatment – identifying tumors and then employing surgery, chemotherapy, radiation, or targeted therapies to eradicate them. While these interventions have saved countless lives and advanced significantly, they often occur after the disease has established itself, frequently leading to aggressive treatments and a persistent risk of recurrence. The CRI’s new focus on prevention and interception marks a crucial paradigm shift, acknowledging a biological reality long understood but historically difficult to act upon: cancer does not emerge instantaneously. Instead, it is a protracted process, unfolding over years, sometimes decades, as cells accumulate mutations and gradually alter their surrounding tissue. Pancreatic cancer, for instance, can spend a decade or more developing from its earliest genetic aberrations before becoming clinically detectable.
This "interval of invisibility" has, until recently, been a black box for oncologists. However, dramatic advancements in molecular genetics, sophisticated early detection methodologies, refined immune monitoring techniques, and detailed precancer mapping are now illuminating this critical window. The analogy to cardiovascular disease is instructive: clinicians manage high blood pressure and elevated cholesterol years before a heart attack, thereby preventing the event itself. Cancer, too, offers a similar window of opportunity. The confluence of novel technologies, a deeper biological understanding of carcinogenesis, and promising early clinical evidence points toward a future where individuals can better understand their inherent risk, collaborate with their healthcare providers to monitor meaningful biological changes, and crucially, intervene far earlier in the disease process.
The CRI CLIP Initiative: Investing in the Future of Oncology
The CLIP initiative at CRI is designed to catalyze this transformation. By concentrating its resources on primary and secondary cancer prevention and interception, CRI aims to foster collaborative, interdisciplinary research that can translate foundational immunological discoveries into tangible clinical benefits. The call for multi-investigator teams underscores the complexity of this challenge, requiring expertise spanning basic immunology, cancer biology, genetics, clinical oncology, epidemiology, and public health. The emphasis on "immune-based approaches" highlights CRI’s longstanding leadership in immunotherapy and its belief that the immune system holds the key to durable prevention.
This strategic direction builds upon CRI’s historical commitment to funding high-risk, high-reward research. By designating a specific scientific theme for CLIP, CRI is signaling a targeted, concentrated effort to accelerate progress in an area with immense potential for public health impact. The institute recognizes that success in prevention and interception demands innovative thinking, robust translational pipelines, and rigorous clinical validation, all of which require substantial, sustained investment.
Three Critical Windows for Intervention
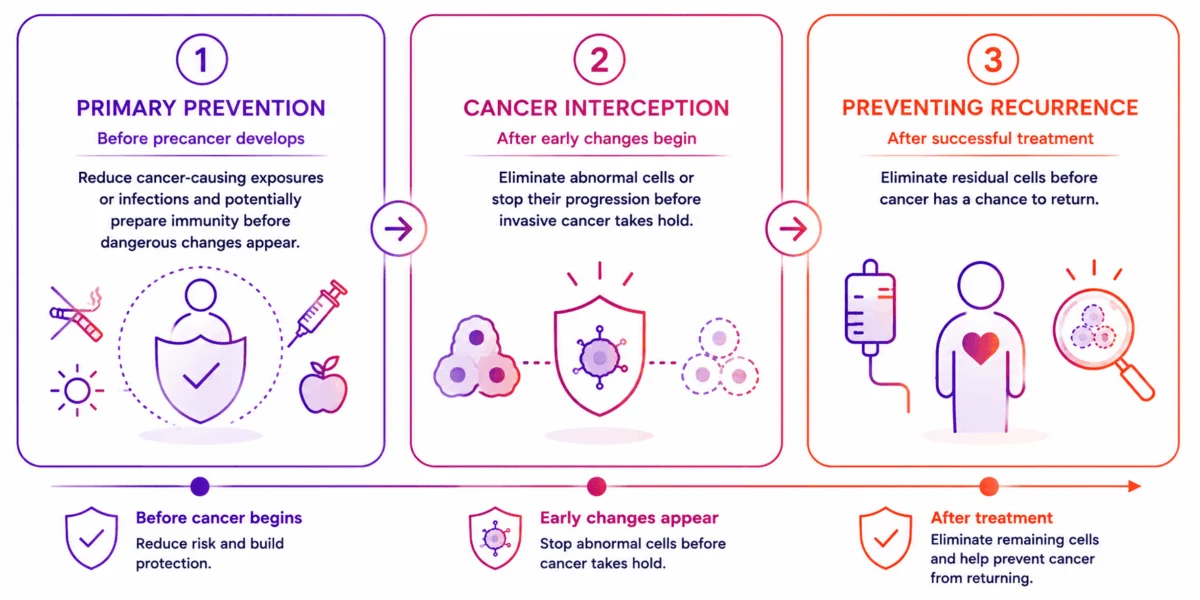
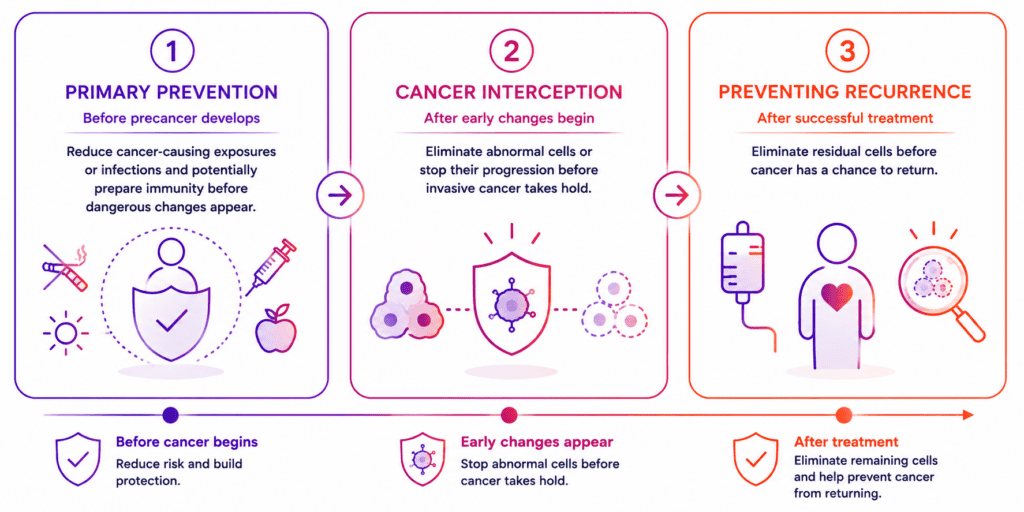
Efforts to prevent cancer from developing or returning can be categorized into three distinct, yet interconnected, "windows" of opportunity:

-
Primary Prevention: This window of action occurs before any precancerous changes have developed. Its goal is to reduce exposure to known cancer-causing agents (e.g., carcinogens, infectious agents) or to bolster the immune system in anticipation of potential dangerous cellular alterations. Examples include lifestyle modifications, vaccination against oncogenic viruses, and potentially novel immunomodulatory strategies to create a "cancer-resistant" immune environment.
-
Cancer Interception: This crucial window opens after the earliest dangerous cellular changes appear, but before invasive cancer fully takes hold. The objective here is to identify and eliminate abnormal cells or halt their progression towards malignancy. This could involve immunotherapies targeting early precancerous lesions, pharmacological interventions to reverse cellular dysregulation, or precise surgical removal of high-risk precancerous tissue.
-
Preventing Recurrence: This window of intervention occurs after successful treatment of an established cancer. The aim is to eliminate any residual microscopic disease that might persist after initial therapy, thereby preventing the cancer from returning. This often involves adjuvant therapies, including immunotherapies, designed to "mop up" lingering cancer cells and train the immune system to recognize and destroy them should they attempt to re-emerge.
Across these three windows, a common thread exists: the abnormal cells are typically absent, limited in number, or microscopic. Critically, the immune system may still retain a significant advantage, being less overwhelmed and suppressed than in cases of advanced, bulky tumors. Acting earlier implies fewer cells to target and fewer barriers to overcome. However, these early changes can be inherently difficult to recognize, and even nascent precancerous lesions can begin to establish an immunosuppressive microenvironment, presenting its own set of challenges.
Historical Precedent: The Power of Immune-Based Prevention
The concept of immune-based cancer prevention is not entirely new; it has a powerful proof of principle in the realm of virally-induced cancers. Vaccines against the Hepatitis B virus (HBV) and the Human Papillomavirus (HPV) stand as monumental successes in primary prevention. HBV vaccination prevents chronic infection, which is a leading cause of liver cancer. Similarly, HPV vaccines prevent infections that cause cervical, anal, oral, and other anogenital cancers.
The global impact of HPV vaccination programs is staggering. Initiatives supported by organizations like Gavi, the Vaccine Alliance, have protected an estimated 86 million girls in lower-income countries, an effort projected to avert a remarkable 1.4 million cervical cancer deaths. Projections suggest that achieving 80 percent global coverage with a one-dose HPV vaccination regimen could prevent more than 50 million cervical cancer cases over the next century.
The Cancer Research Institute played a pivotal role in advancing this science. Beginning in 1999, CRI provided crucial support to Dr. Ian H. Frazer, whose pioneering work on virus-like particles was instrumental in the development of the technology behind Gardasil®, a widely used HPV vaccine. This historical commitment underscores CRI’s foresight and its capacity to identify and nurture transformative research.
Beyond viral prevention, other established strategies demonstrate the efficacy of early intervention. Routine colonoscopies that detect and remove precancerous polyps significantly lower colorectal cancer incidence and mortality. Daily aspirin therapy has been shown to reduce colorectal cancer risk in individuals with Lynch syndrome, a hereditary condition. Prophylactic removal of ovaries and fallopian tubes drastically reduces ovarian cancer risk in women carrying BRCA mutations. These examples firmly establish the principle: intervening before invasive cancer emerges can, indeed, save lives. The current frontier involves extending this principle to non-viral cancers by leveraging and training the immune system to recognize and eliminate precancerous or residual cancer cells.
Emerging Frontiers: Immunotherapy in Precancerous States
Recent clinical trials offer both promising signals and crucial lessons regarding the application of immunotherapy in cancer interception.
One early trial investigating a vaccine targeting MUC1, a protein often altered on precancerous colon growths, highlighted both the potential and the complexities. While the vaccine produced an immune response in only one in four recipients and did not significantly reduce recurrence overall, a deeper analysis revealed a critical insight: among those who developed a lasting immune response, recurrence rates were 38 percentage points lower compared to the placebo group. Interestingly, non-responders exhibited a higher baseline of immune-suppressing cells and inflammatory signals even before vaccination. This suggests that successful interception may hinge not only on identifying the right target but also on ensuring the immune system is "primed" and capable of responding effectively. Understanding an individual’s baseline immune state could become crucial for patient selection and determining whether immune suppression needs to be addressed prior to intervention.
Another trial explored nivolumab, an approved immunotherapy, in treating high-risk mouth lesions. The drug successfully shrank lesions in approximately one-third of participants. However, some responders still progressed to invasive cancer, and a notable one in five experienced severe immune-related side effects. This trial yielded an important lesson: lesion shrinkage, while encouraging, does not automatically equate to cancer prevention. For individuals who do not yet have cancer, a successful intervention must demonstrably reduce future cancer risk while meticulously safeguarding their current health and quality of life. The risk-benefit calculus for prevention is inherently different from that for treating established disease.
Despite these challenges, clear early targets offer a compelling path forward. Over 90 percent of the most common form of pancreatic cancer, along with many of its precancerous lesions, harbor a specific mutation in the KRAS gene. A vaccine designed to target six common KRAS mutations elicited an immune response in 90 percent of 20 high-risk participants, with vaccine-induced immune cells detectable for up to two years. While this study did not directly test prevention, it answered two foundational questions: the vaccine was safe and capable of generating a durable immune response. A subsequent group of participants awaiting surgery will help determine if these immune cells can effectively reach the precancerous lesions, where their action is required.
Lynch syndrome, an inherited condition predisposing individuals to colorectal and several other cancers, presents a similar strategic opportunity. This syndrome disrupts the cell’s DNA proofreading system, leading to recurrent mutations and creating shared vaccine targets. A vaccine designed to target 209 such mutations generated an immune response in every participant. The next crucial step is to determine if these immune responses translate into actual cancer prevention. Collectively, these studies demonstrate the feasibility of generating durable, targeted immune responses in individuals at elevated risk. The immense work ahead lies in translating these responses into effective prevention strategies.
Navigating the Challenges Ahead
The field of cancer prevention and interception is defined by several interconnected and complex challenges that require a concerted, multidisciplinary effort:
-
Identifying and Validating Early Targets: The success of any preventive or interceptive strategy hinges on identifying specific molecular or cellular targets that are present early in carcinogenesis, are highly specific to precancerous cells, and are amenable to immune attack. These targets must be distinct enough from healthy tissue to minimize off-target effects.
-
Developing Reliable Biomarkers: Accurate biomarkers are essential for identifying individuals at high risk, detecting precancerous lesions, monitoring the efficacy of interventions, and predicting who will respond to therapy. These biomarkers need to be sensitive, specific, and non-invasive.
-
Establishing Relevant Preclinical Models: Animal and in vitro models must accurately reflect human precancerous conditions and the early stages of immune evasion. Developing models that faithfully recapitulate the complexities of human precancer progression and immune responses is crucial for testing novel interventions.

-
Understanding the Immune Microenvironment of Precancer: The immune system’s state and activity within precancerous lesions can vary significantly. Some lesions might be immunologically "cold" or suppressive, while others might be more amenable to immune activation. A deeper understanding of these microenvironments is critical for designing effective immune-based interventions.
-
Designing and Executing Rigorous Clinical Trials: Clinical trials for prevention and interception face unique challenges, including the need for large cohorts, long follow-up periods, and careful consideration of the risk-benefit ratio in healthy or asymptomatic populations. Ethical considerations, particularly around informed consent and potential side effects in individuals who may never develop invasive cancer, are paramount.
These challenges are fundamentally inseparable. A potential target is only relevant if it appears early enough in the disease process. A laboratory model is only useful if it accurately reflects human precancer. A biomarker is only valuable if it can reliably guide intervention or demonstrate its effectiveness. True progress in this field will demand a seamless integration of mechanistic discovery with rigorous clinical application.
Encouragingly, progress is already tangible, particularly in the "preventing recurrence" window. In August 2026, Merck and Moderna announced promising results from a large Phase III trial, where a personalized mRNA vaccine tailored to each patient’s tumor mutations, when combined with pembrolizumab (an approved immunotherapy), significantly reduced the risk of melanoma recurrence after surgery. While full results are still pending publication, this finding provides strong support for immune-based prevention strategies when any remaining disease is microscopic, offering a blueprint for future interventions in other cancer types.
The Transformative Opportunity Ahead
The Cancer Research Institute firmly believes that cancer interception has the potential to fundamentally reshape cancer care. By shifting a greater proportion of resources and effort from treating established disease to preventing cancer from taking hold or returning, we can mitigate suffering, reduce the burden on healthcare systems, and ultimately save more lives. Realizing this ambitious vision necessitates an unprecedented level of team science, integrating cutting-edge fundamental immunology and cancer biology with advanced early detection technologies and meticulously designed clinical trials.
CRI is resolute in its commitment to investing in the visionary scientists, fostering critical collaborations, and supporting the translational research pipelines required to transform early promise into life-saving interventions. The window before cancer becomes clinically manifest is a tangible reality. With rigorous scientific inquiry, unwavering commitment, and strategic investment, humanity can learn to leverage this window to stop more cancers before individuals ever have to confront the disease, or face its daunting return. This new era of proactive oncology holds the promise of a healthier future, where prevention stands alongside treatment as a cornerstone of cancer care.
