
 By Gilang Cahya
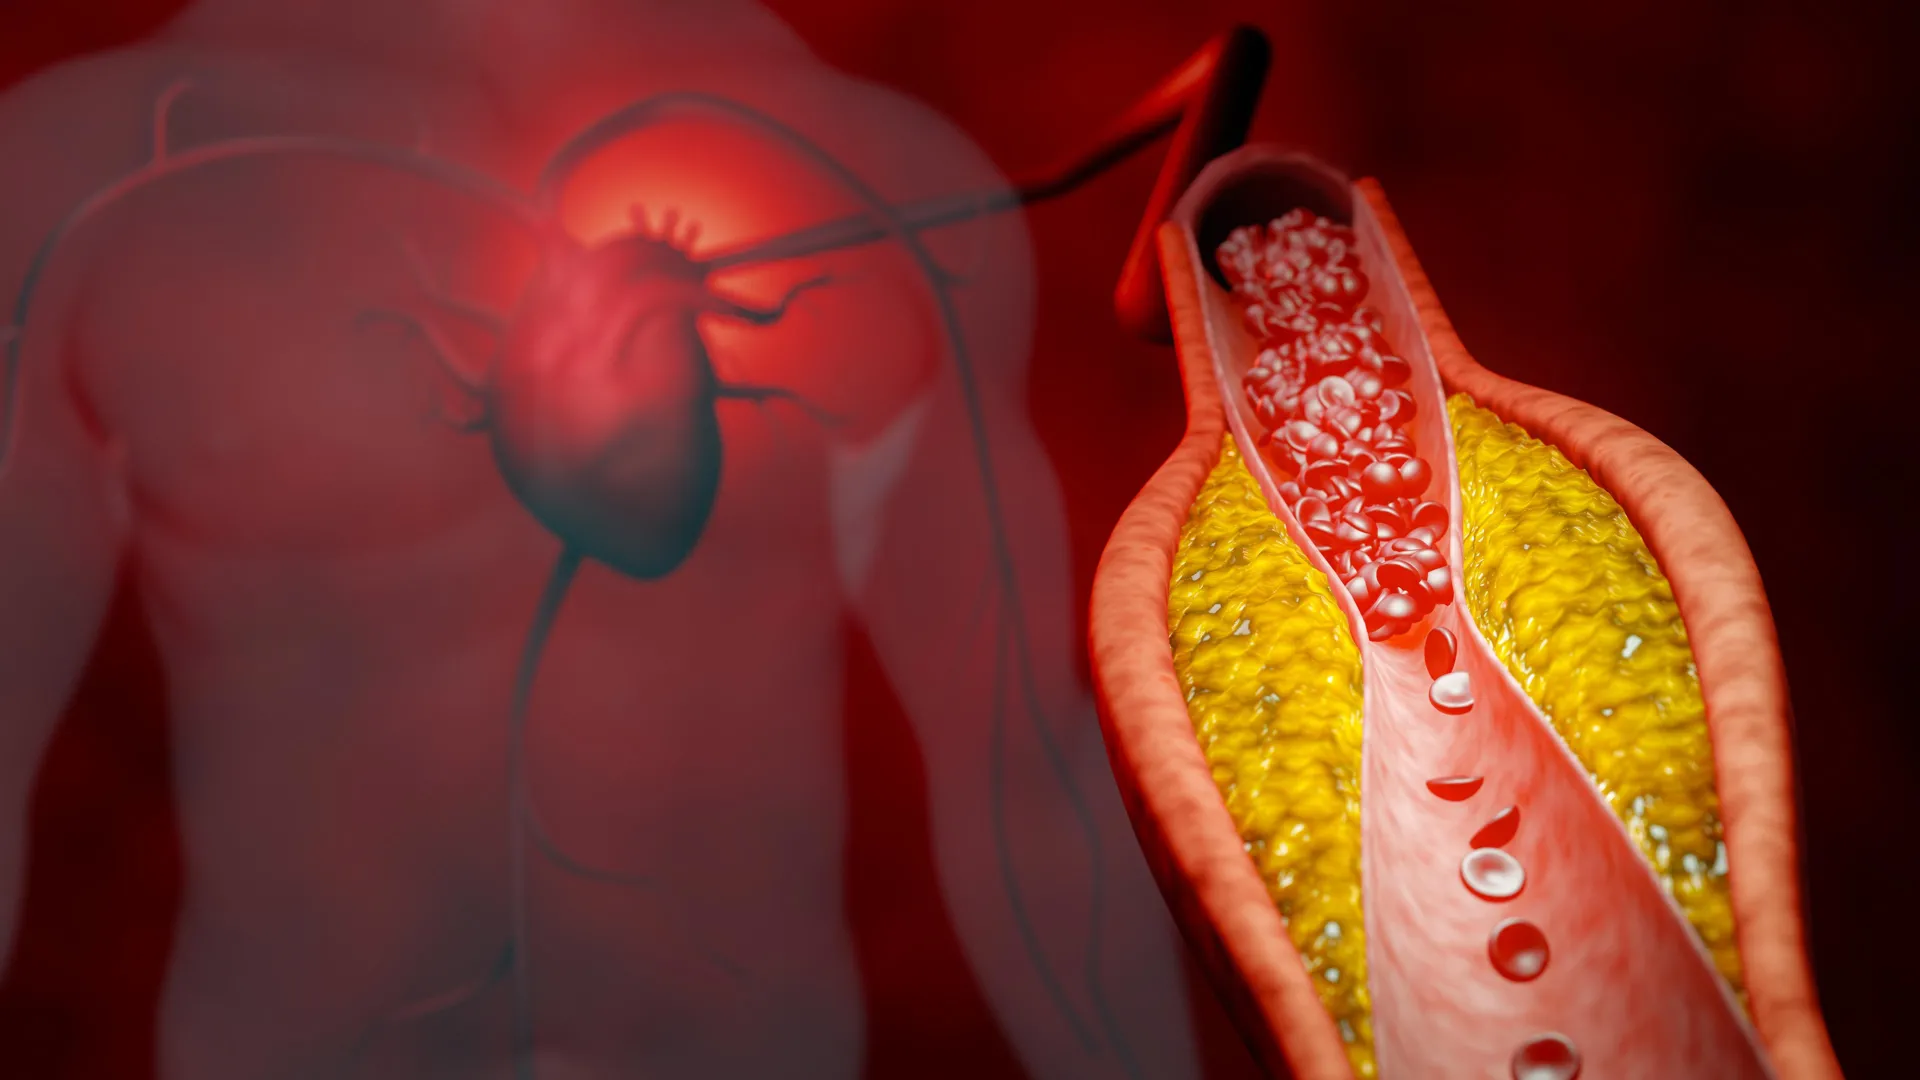
Millions of Americans undergo annual blood tests to measure their low-density lipoprotein (LDL) cholesterol, commonly referred to as "bad" cholesterol. This routine screening has long been a cornerstone of cardiovascular risk assessment and management. However, groundbreaking research emerging from Northwestern Medicine suggests that an alternative marker, apolipoprotein B (apoB), may offer a more precise and effective method for identifying individuals who stand to benefit most from more aggressive treatment strategies aimed at mitigating the risk of heart attacks and strokes. This new body of evidence, published in the prestigious JAMA, indicates that focusing on apoB levels could lead to better patient outcomes and a more efficient allocation of healthcare resources in the ongoing battle against heart disease, the leading cause of death in the United States.
The Limitations of Current Cholesterol Metrics
For decades, healthcare professionals have relied on LDL and non-high-density lipoprotein (non-HDL) cholesterol levels to guide decisions regarding the initiation and intensification of cholesterol-lowering therapies. These tests provide valuable insights into the amount of cholesterol circulating in the bloodstream. LDL cholesterol, in particular, is known for its propensity to contribute to the buildup of plaque within artery walls, a process that can lead to narrowed arteries, restricted blood flow, and an increased risk of cardiovascular events. Non-HDL cholesterol offers a broader picture by encompassing all cholesterol-carrying particles that are not HDL, which are generally considered protective.
Despite their widespread use and established utility, these traditional metrics do not always fully capture the complexity of an individual’s cardiovascular risk profile. The underlying issue, according to the Northwestern study, lies in how these tests measure cholesterol. LDL and non-HDL cholesterol tests quantify the amount of cholesterol itself. However, it is the number of particles that carry this cholesterol that directly contributes to the pathological processes leading to atherosclerosis.
ApoB: A More Direct Measure of Harmful Particles
Apolipoprotein B (apoB) offers a distinct advantage in this regard. Instead of measuring the cholesterol content, apoB measures the actual number of apolipoprotein B-containing lipoproteins in the blood. These lipoproteins are the primary carriers of cholesterol that can become trapped in artery walls, initiating and accelerating the formation of atherosclerotic plaques. As Ciaran Kohli-Lynch, assistant professor of preventive medicine at Northwestern University Feinberg School of Medicine and lead author of the study, explained, "Research strongly shows that apolipoprotein B (apoB) is better at identifying who is at risk, because it counts the total number of harmful particles in the blood." This direct measurement of the number of atherogenic particles makes apoB a more sensitive and specific indicator of cardiovascular risk than simply measuring cholesterol levels.
The implications of this distinction are significant. An individual might have a seemingly acceptable LDL cholesterol level, but if they possess a high number of apoB-containing particles, their risk of plaque buildup and subsequent cardiovascular events could still be substantial. Conversely, someone with a higher LDL level but fewer apoB particles might be at a lower risk than predicted by their LDL alone. Therefore, using apoB as a guiding metric allows for a more nuanced and accurate assessment of an individual’s true cardiovascular threat.
The Study’s Design and Key Findings
The research team embarked on a comprehensive analysis to rigorously compare the effectiveness and cost-effectiveness of using apoB versus traditional LDL and non-HDL cholesterol levels in guiding cholesterol-lowering therapy. To achieve this, they employed a sophisticated computer simulation model. This model was designed to represent a cohort of 250,000 U.S. adults who were deemed eligible for statin therapy but did not have pre-existing cardiovascular disease. This demographic is crucial as it represents a primary prevention population, where early and accurate risk assessment is paramount.
The simulation meticulously tracked three distinct strategies for guiding treatment intensification when patients failed to meet their target lipid levels:
- LDL Cholesterol-Guided Therapy: This approach adheres to current standard practices, where treatment intensity is adjusted based on achieving specific LDL cholesterol goals.
- Non-HDL Cholesterol-Guided Therapy: This strategy utilizes non-HDL cholesterol levels as the primary determinant for treatment adjustments.
- Apolipoprotein B (apoB)-Guided Therapy: This novel approach centers on achieving target apoB levels to guide treatment intensification.
In all three scenarios, when patients did not reach their assigned lipid targets, the treatment regimen was escalated. This typically involved transitioning to more potent statin medications or, if necessary, adding other classes of lipid-lowering drugs such as ezetimibe. The computer model then projected the long-term outcomes for each of these strategies over a simulated lifetime. The researchers meticulously estimated key health metrics, including the incidence of heart attacks and strokes, overall life expectancy, quality of life, and the associated healthcare costs.
The results of this extensive simulation were compelling and consistently favored the apoB-guided approach. The study unequivocally found that using apoB to guide cholesterol treatment intensification led to superior health outcomes. Specifically, it was associated with a greater prevention of cardiovascular events, including heart attacks and strokes, compared to strategies based on LDL or non-HDL cholesterol. Crucially, these improved health benefits were achieved at a cost that represented good value for U.S. healthcare payers, indicating a favorable cost-effectiveness profile.
"We found that apoB testing to intensify cholesterol-lowering medication would prevent more heart attacks and strokes than current practice, and that these health benefits were achieved at a cost that represents good value for U.S. healthcare payers," stated Kohli-Lynch, underscoring the dual advantage of improved health and economic efficiency. He further highlighted that this is the first comprehensive analysis to demonstrate that employing apoB to guide cholesterol treatment is not only more effective but also cost-effective.
The Economic and Societal Burden of Heart Disease
Heart disease remains an overwhelming public health challenge in the United States, consistently ranking as the leading cause of death. Beyond the devastating human toll, it imposes an immense financial burden on the healthcare system. Billions of dollars are spent annually on treating heart disease and its complications. The underlying pathological mechanism, atherosclerosis, is a chronic and progressive disease where the gradual accumulation of cholesterol-laden plaques within the arteries can severely restrict blood flow. This blockage can lead to a range of serious conditions, from angina (chest pain) to myocardial infarction (heart attack) and cerebrovascular accidents (stroke), often with life-altering consequences for patients and their families.
The study’s findings, therefore, hold significant promise for potentially reducing this burden by enabling more precise and proactive interventions. By identifying individuals at higher risk earlier and more accurately through apoB testing, clinicians can initiate or intensify appropriate lipid-lowering therapies sooner, thereby slowing or even preventing the progression of atherosclerosis.
Current Landscape and Future Implications of Cholesterol Management
The emergence of these findings coincides with a dynamic period in cardiovascular medicine, marked by the availability of a growing arsenal of effective cholesterol-lowering medications. Furthermore, recent updates to clinical guidelines by major medical organizations, such as the American Heart Association and 10 other leading medical bodies, have signaled a shift towards earlier initiation of cholesterol-lowering therapy for a broader segment of the population, including younger individuals and those with lower baseline cardiovascular risk.
"This means it is increasingly important to accurately identify who would benefit most from intensive treatment," emphasized Kohli-Lynch. The evolving treatment landscape necessitates more precise diagnostic tools to ensure that interventions are targeted to those who will derive the greatest benefit, avoiding unnecessary treatments for those at lower risk and ensuring adequate treatment for those at higher risk. The Northwestern study provides strong evidence that apoB testing can fulfill this critical need.
Barriers to ApoB Adoption and the Path Forward
Despite the accumulating scientific evidence supporting the superiority of apoB testing, its adoption into routine clinical practice has been slower than might be expected. One of the primary reasons cited for this hesitancy is the perceived increase in cost and inconvenience associated with an additional blood test beyond the standard lipid panel. Traditionally, measuring apoB requires a separate laboratory analysis, which can incur additional expenses for both patients and healthcare providers and may require an additional visit or phlebotomy session.
Kohli-Lynch and his colleagues directly addressed this concern within their study. "Our study asked: Is it worth spending extra money to use apoB instead of LDL to guide treatment intensification?" he stated. The comprehensive cost-effectiveness analysis provided a clear answer: yes, it is. The improved clinical outcomes and the subsequent reduction in costly cardiovascular events and associated long-term care outweigh the incremental cost of the apoB test. This suggests that a shift in reimbursement policies and clinical practice guidelines could facilitate wider adoption.
The implications of this research extend beyond individual patient care. Widespread adoption of apoB testing could lead to a more efficient allocation of healthcare resources, potentially reducing overall healthcare expenditures by preventing a greater number of costly cardiovascular events. It could also foster a more personalized approach to cardiovascular risk management, moving away from a one-size-fits-all model based on broad cholesterol categories towards a more precise, particle-based risk assessment.
Expert Reactions and Broader Context
While direct quotes from external parties were not included in the original source, the implications of this study are likely to be met with considerable interest and discussion within the cardiovascular research and clinical communities. Leading cardiologists and lipidologists have been advocating for greater utilization of apoB for years, citing its mechanistic relevance to atherosclerosis. This study provides robust data to support their long-standing arguments and may serve as a catalyst for change in clinical practice guidelines and physician behavior.
The study, titled "Cost-Effectiveness of ApoB, Non-HDL-C, and LDL-C Goals for Primary Prevention Lipid-Lowering Therapy," was supported by a grant from the American Heart Association, underscoring the importance that this leading cardiovascular organization places on advancing research in this critical area. The collaborative efforts of Northwestern coauthors, including Drs. John Wilkins and Samuel Luebbe, further strengthen the validity and impact of this research.
In conclusion, the Northwestern Medicine study represents a significant step forward in the understanding and management of cardiovascular disease. By demonstrating the superior effectiveness and cost-effectiveness of apolipoprotein B testing in guiding cholesterol-lowering therapy, this research offers a compelling vision for the future of heart disease prevention. As the medical community continues to refine its strategies for combating this pervasive illness, the insights gleaned from this study are poised to play a pivotal role in ensuring that millions of Americans receive the most accurate and effective care to protect their cardiovascular health.
