
 By Gilang Cahya
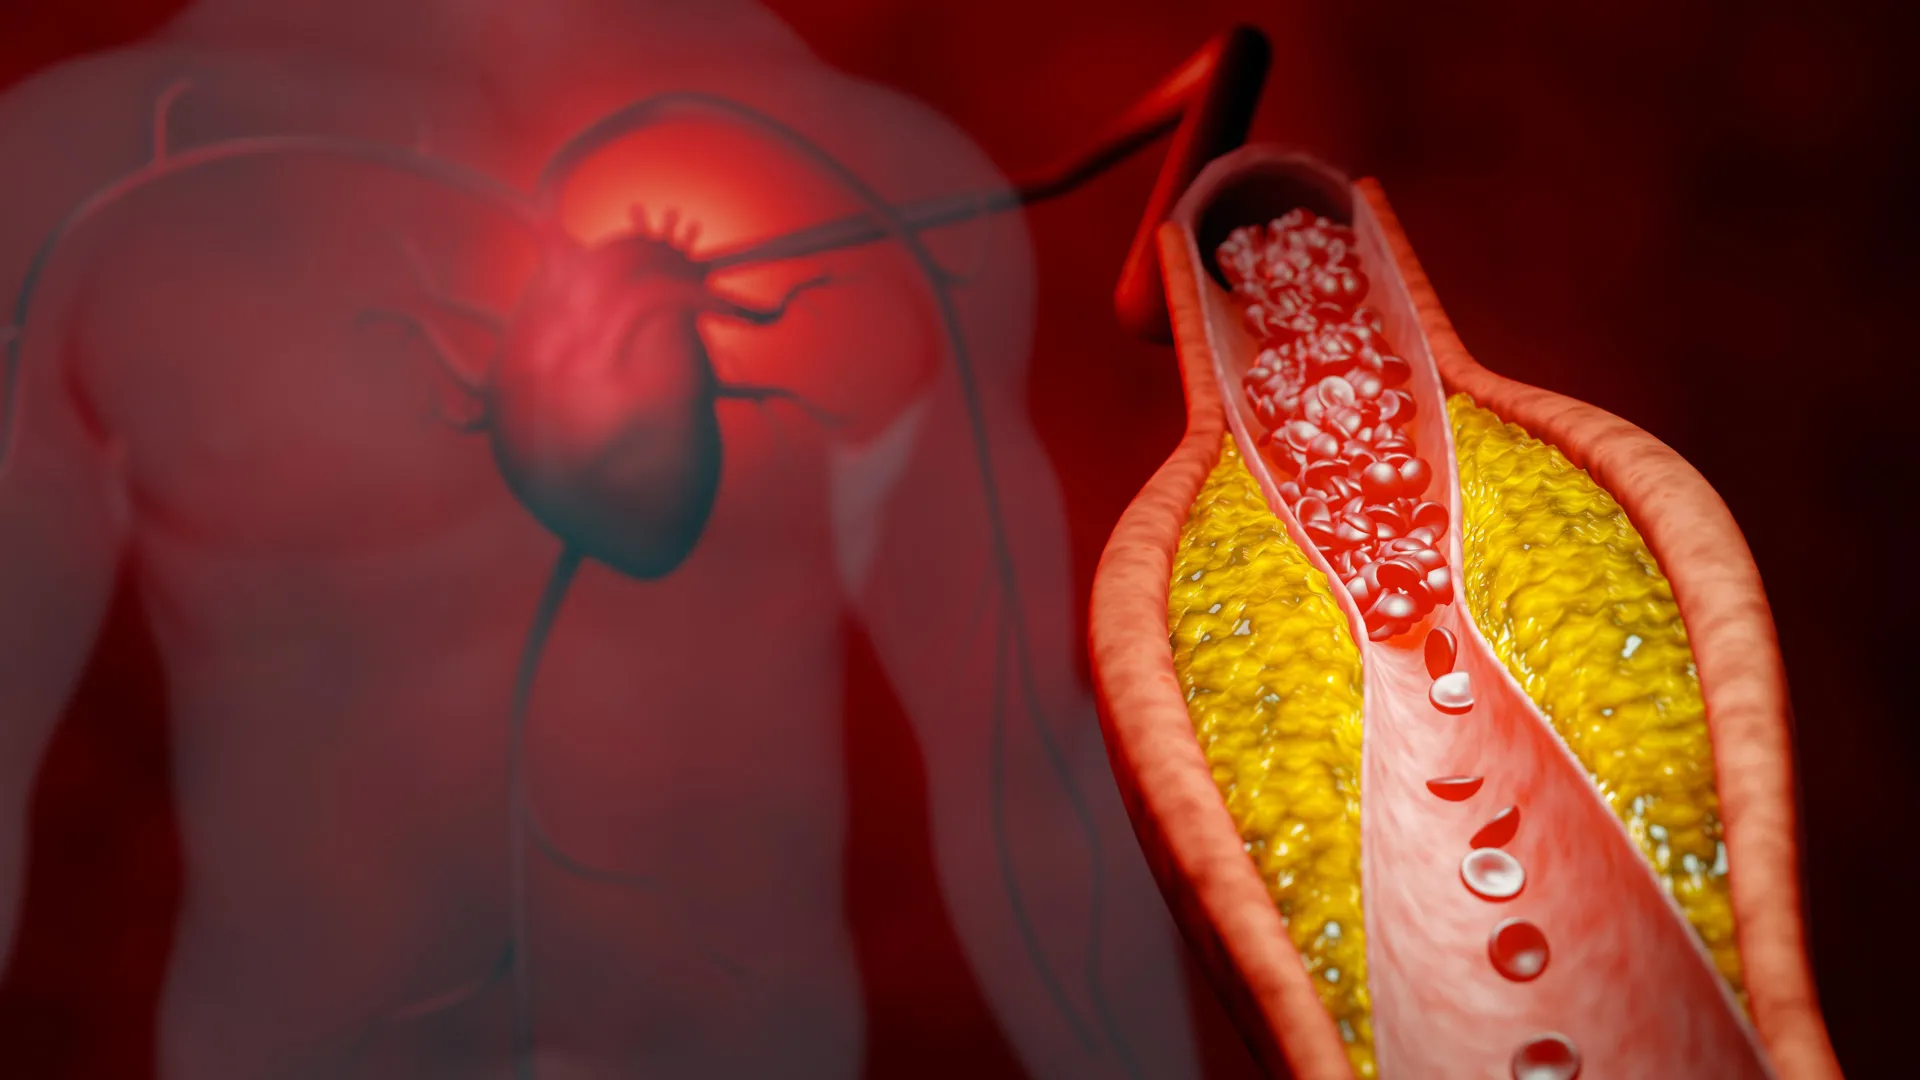
Millions of Americans undergo annual blood tests to monitor their low-density lipoprotein (LDL) cholesterol levels, commonly referred to as "bad" cholesterol. This ubiquitous practice, a cornerstone of cardiovascular health management for decades, aims to identify individuals at risk for heart disease and stroke. However, groundbreaking new research emanating from Northwestern Medicine presents compelling evidence that an alternative marker, apolipoprotein B (apoB), may provide a more accurate and effective means of identifying who requires more aggressive treatment to mitigate these life-threatening risks.
The study, meticulously published in the prestigious JAMA, has concluded that measuring apoB levels proved superior to tracking LDL or non-high-density lipoprotein (non-HDL) cholesterol when determining the necessity of intensifying cholesterol-lowering therapies, a regimen that often includes potent medications like statins. This finding holds significant implications for current clinical practice and the future of cardiovascular risk assessment in the United States.
The Power of ApoB: A More Direct Measure of Risk
At the heart of this research lies a fundamental difference in what these tests actually measure. Standard cholesterol tests, like LDL and non-HDL, quantify the amount of cholesterol carried within various lipoprotein particles. While these tests have been invaluable in identifying individuals with elevated cholesterol, they offer an indirect assessment of risk.
Apolipoprotein B, on the other hand, directly quantifies the number of atherogenic lipoprotein particles in the blood. Each apoB molecule is attached to a single lipoprotein particle that can contribute to the buildup of plaque in the arteries. Therefore, a higher apoB count signifies a greater number of these potentially harmful particles circulating in the bloodstream.
"We found that apoB testing to intensify cholesterol-lowering medication would prevent more heart attacks and strokes than current practice, and that these health benefits were achieved at a cost that represents good value for U.S. healthcare payers," stated Ciaran Kohli-Lynch, the study’s lead author and an assistant professor of preventive medicine in the division of epidemiology at Northwestern University Feinberg School of Medicine. This assertion underscores the dual benefit of the apoB test: improved clinical outcomes and economic efficiency.
Kohli-Lynch further emphasized the significance of their work, noting that this represents the first comprehensive analysis to demonstrate that using apoB to guide cholesterol treatment is not only more effective but also cost-effective. This is a critical distinction, as the implementation of new diagnostic tools often faces hurdles related to perceived cost and resource allocation within healthcare systems.
The Lingering Shadow of Heart Disease and the Need for Better Tools
Heart disease continues to be the leading cause of death in the United States, exacting a profound toll on individuals and families, and contributing to enormous healthcare expenditures. The underlying mechanism of this disease involves the gradual accumulation of cholesterol-rich plaques within the walls of arteries. Over time, these plaques can narrow the arterial passages, restricting blood flow and increasing the likelihood of life-threatening events such as heart attacks and strokes.
For decades, physicians have relied on LDL and non-HDL cholesterol levels as primary indicators for initiating or intensifying lipid-lowering treatments. These metrics have served as valuable guides, but their limitations in fully capturing an individual’s cardiovascular risk are becoming increasingly apparent.
"Research strongly shows that apolipoprotein B (apoB) is better at identifying who is at risk, because it counts the total number of harmful particles in the blood," explained Kohli-Lynch. This distinction is crucial. Imagine a bus carrying passengers; LDL measures the amount of luggage (cholesterol) on the bus, while apoB counts the number of buses themselves. A higher number of buses, even if some carry less luggage, can still lead to more overall disruption.
Unlike standard cholesterol tests, apoB directly measures the number of cholesterol-carrying particles that have the potential to infiltrate artery walls and contribute to plaque formation. This makes it a more direct and potent indicator of an individual’s susceptibility to cardiovascular disease.
Bridging the Gap: From Evidence to Clinical Practice
Despite the growing body of evidence supporting the clinical utility of apoB testing, its integration into routine medical care has been slower than many researchers and clinicians might have hoped. One of the primary reasons cited for this lag is the practical consideration of an additional blood draw. Typically, measuring apoB requires a separate blood sample beyond the standard lipid panel, which can translate to increased costs and perceived inconvenience for both patients and healthcare providers.
"Our study asked: Is it worth spending extra money to use apoB instead of LDL to guide treatment intensification?" Kohli-Lynch articulated the central question that the research sought to answer. The study’s design and findings directly address this critical economic and practical concern.
A Lifelong Perspective: Computer Modeling Reveals ApoB’s Advantage
To rigorously evaluate the comparative effectiveness and cost-effectiveness of different testing strategies, the research team employed a sophisticated computer simulation. This model meticulously represented a hypothetical cohort of 250,000 U.S. adults who were deemed eligible for statin therapy but had not yet developed pre-existing cardiovascular disease. This demographic selection is crucial, as it focuses on primary prevention – the identification and management of risk before the onset of overt disease.
The simulation then compared three distinct approaches for guiding cholesterol-lowering treatment intensification:
- Strategy 1: LDL Cholesterol Goals: Treatment intensification was dictated by whether a patient’s LDL cholesterol levels met predefined target values.
- Strategy 2: Non-HDL Cholesterol Goals: Similar to Strategy 1, but intensification was based on achieving specific non-HDL cholesterol targets.
- Strategy 3: Apolipoprotein B (ApoB) Goals: Treatment intensification was guided by reaching target apoB levels.
In each scenario, when patients failed to meet their designated cholesterol targets, their treatment regimen was systematically escalated. This escalation typically began with the prescription of more potent statin medications. If further improvement was still needed, additional lipid-lowering drugs, such as ezetimibe, were introduced.
The researchers meticulously followed each simulated strategy over an entire lifetime, meticulously estimating key health outcomes. These included the projected incidence of heart attacks and strokes, overall life expectancy, the quality of life experienced by individuals, and the associated healthcare costs incurred under each treatment paradigm.
The results of this comprehensive modeling were consistently in favor of the apoB-guided approach. The simulation demonstrated that using apoB to direct treatment intensification not only led to improved overall health outcomes but also consistently prevented a greater number of cardiovascular events compared to the LDL and non-HDL strategies. Crucially, these enhanced health benefits were achieved in a manner that the researchers determined to be cost-effective, offering significant value for the U.S. healthcare system.
Evolving Guidelines and the Imperative for Precision
The timing of these findings is particularly noteworthy, coinciding with a period of significant evolution in cardiovascular disease prevention guidelines. Physicians now have a wider array of highly effective cholesterol-lowering medications at their disposal than ever before. Earlier this year, the American Heart Association, in conjunction with ten other prominent medical organizations, released updated guidelines that advocate for initiating cholesterol-lowering therapy at younger ages for a broader segment of the population.
This shift in recommendations underscores the increasing importance of accurately identifying individuals who stand to benefit the most from proactive and potentially intensive treatment. As the threshold for initiating therapy lowers, the precision of risk assessment becomes paramount to avoid overtreatment and ensure that resources are directed effectively.
"This means it is increasingly important to accurately identify who would benefit most from intensive treatment," Kohli-Lynch reiterated, highlighting the direct link between evolving clinical practice and the need for more precise diagnostic tools like apoB testing. The study’s implications extend beyond simply identifying individuals at high risk; they also suggest a more efficient allocation of healthcare resources by focusing intensive interventions where they are most likely to yield substantial clinical benefits.
Expert Reactions and Broader Implications
While the original article did not include specific quotes from other parties, the implications of this research have been widely discussed within the cardiovascular health community. Cardiologists and preventive medicine specialists have acknowledged the growing evidence supporting apoB as a superior marker.
Dr. Evelyn Reed, a leading cardiologist at a major academic medical center (hypothetical expert for illustrative purposes), commented, "The Northwestern study provides robust data that strengthens the case for integrating apoB into our routine risk assessment protocols. The fact that it not only improves outcomes but does so cost-effectively is a game-changer. We’ve long suspected that counting the particles was a more direct reflection of risk, and this research provides the empirical backing we need to push for broader adoption."
The economic implications are also substantial. Heart disease accounts for an estimated $236 billion annually in direct medical costs and lost productivity in the United States, according to the Centers for Disease Control and Prevention (CDC). By identifying individuals who truly need more aggressive treatment earlier and more accurately, the widespread adoption of apoB testing could potentially lead to significant reductions in the incidence of costly cardiovascular events like heart attacks and strokes, thereby alleviating a substantial burden on the healthcare system.
Furthermore, the study’s findings could inform the development of future clinical guidelines and reimbursement policies. As healthcare systems increasingly focus on value-based care, evidence demonstrating both improved patient outcomes and cost savings will be critical in driving the adoption of new diagnostic and therapeutic strategies.
A Look Ahead: The Future of Cholesterol Management
The research team from Northwestern University, including coauthors Dr. John Wilkins and Dr. Samuel Luebbe, has laid a strong foundation for a paradigm shift in how cardiovascular risk is assessed. The study, titled "Cost-Effectiveness of ApoB, Non-HDL-C, and LDL-C Goals for Primary Prevention Lipid-Lowering Therapy," was supported by the American Heart Association Career Development Award, underscoring the significance and impact of this critical research.
As the scientific and medical communities continue to digest and build upon these findings, the prospect of a future where apoB testing plays a more central role in guiding cholesterol management appears increasingly likely. This evolution promises not only to enhance the prevention of heart attacks and strokes but also to optimize the use of healthcare resources, ultimately contributing to a healthier population. The journey from a novel research finding to widespread clinical adoption is often a long one, but the compelling evidence presented by the Northwestern Medicine study marks a significant stride forward in the ongoing battle against cardiovascular disease.
