
 By Gilang Cahya
Millions of Americans undergo annual blood tests to assess their levels of low-density lipoprotein (LDL) cholesterol, commonly referred to as "bad" cholesterol. This ubiquitous screening tool has long been a cornerstone of cardiovascular risk assessment and management. However, groundbreaking new research emerging from Northwestern Medicine indicates that a different metric, apolipoprotein B (apoB), may offer a more precise and effective method for identifying individuals who would benefit most from intensified cholesterol-lowering therapies, thereby potentially preventing a greater number of heart attacks and strokes.
The study, meticulously detailed in the esteemed journal JAMA, conducted a comprehensive analysis comparing the efficacy of apoB measurements against traditional LDL and non-high-density lipoprotein (non-HDL) cholesterol levels. The findings strongly suggest that apoB is a superior predictor of cardiovascular risk and a more accurate guide for determining when to escalate treatment, including the prescription of statins and other potent lipid-lowering medications.
"Our findings are quite compelling," stated Ciaran Kohli-Lynch, the study’s lead author and an assistant professor of preventive medicine in the division of epidemiology at Northwestern University Feinberg School of Medicine. "We observed that utilizing apoB testing to guide the intensification of cholesterol-lowering medication would lead to a significant reduction in heart attacks and strokes compared to current clinical practices. Crucially, these substantial health benefits are achievable at a cost that represents excellent value for U.S. healthcare payers."
This research marks a significant milestone as it presents the first comprehensive analysis to demonstrate not only the superior clinical utility of apoB in guiding cholesterol treatment but also its cost-effectiveness. This dual finding addresses a critical need in a healthcare landscape grappling with the immense burden of heart disease.
The Enduring Challenge of Heart Disease in the United States
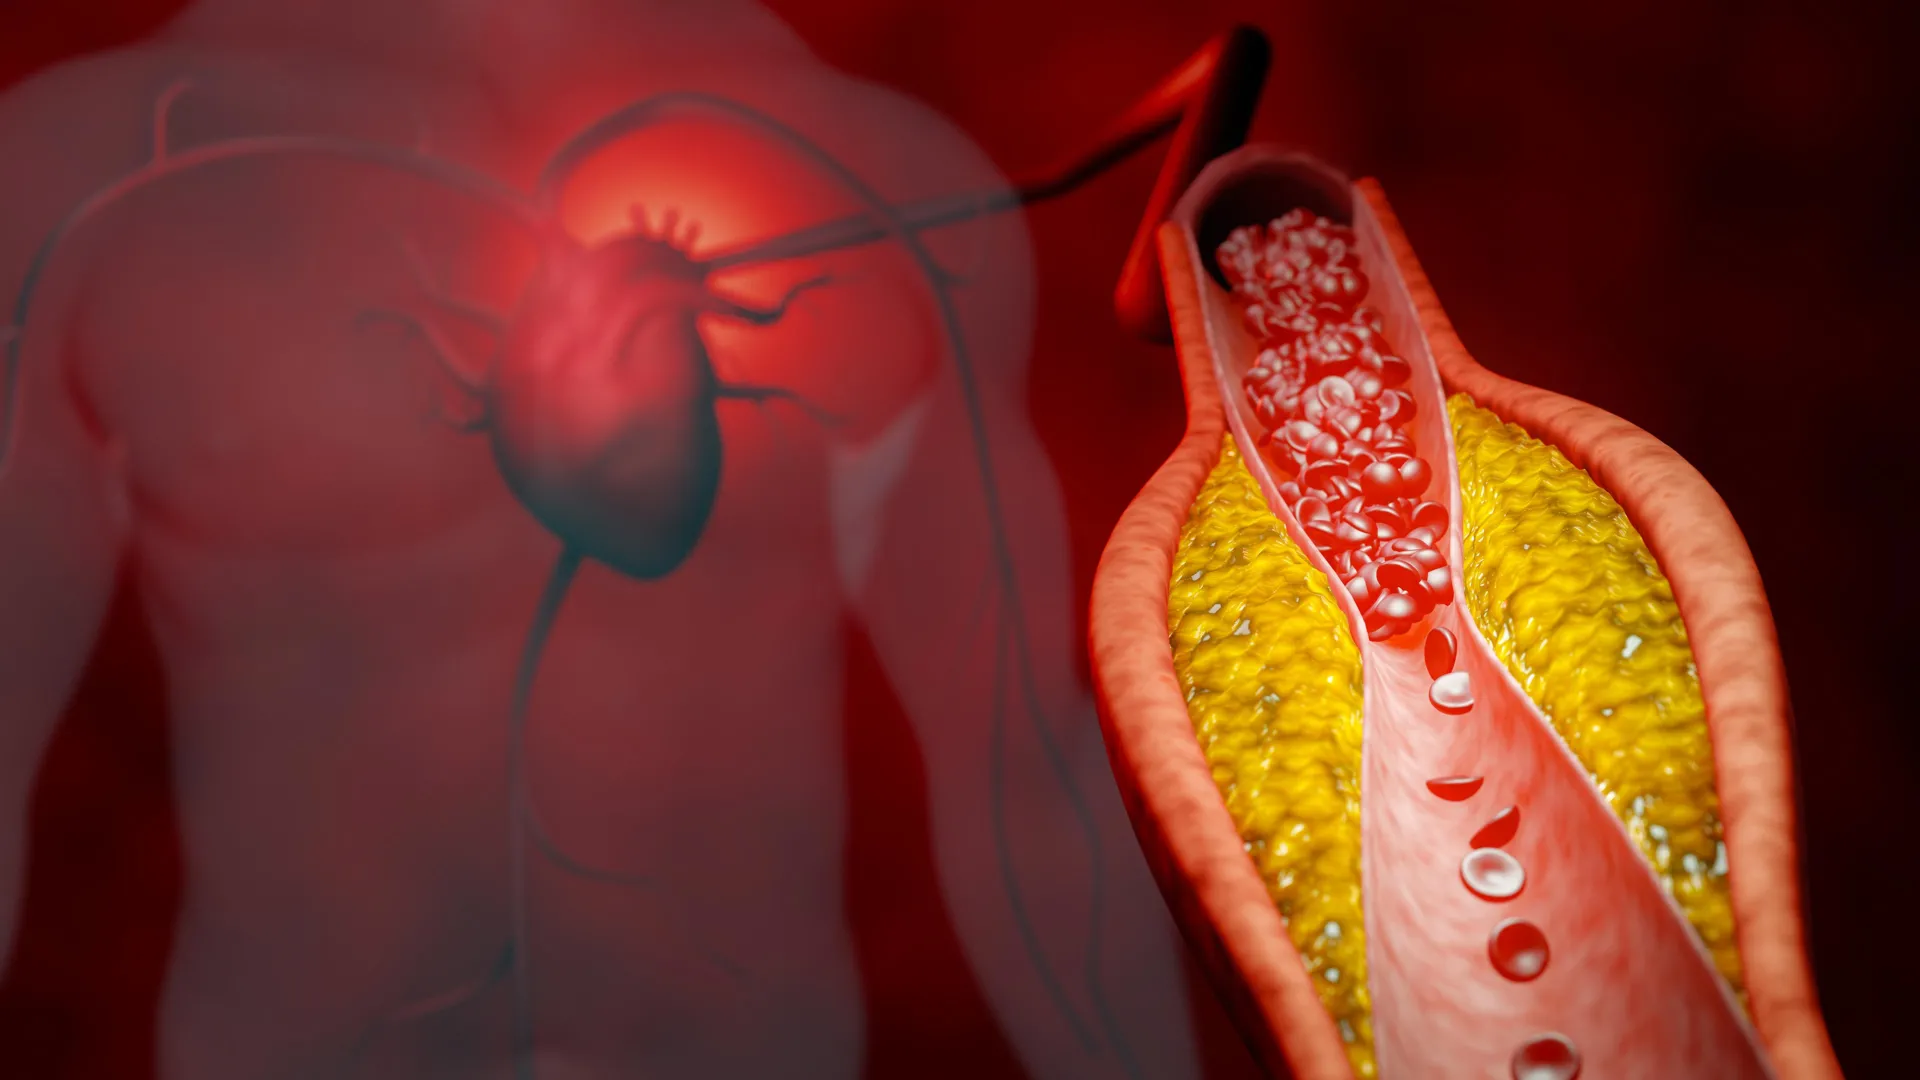
Heart disease continues to hold its position as the leading cause of mortality in the United States, exacting a devastating toll on lives and contributing to staggering healthcare expenditures. The underlying mechanism of this pervasive disease involves the gradual accumulation of cholesterol-laden particles within the arterial walls. Over time, these particles can transform into atherosclerotic plaques, narrowing the arteries, restricting blood flow, and significantly increasing the risk of life-threatening events such as heart attacks and strokes.
For decades, clinicians have relied on LDL cholesterol and non-HDL cholesterol levels as primary indicators for initiating or intensifying lipid-lowering interventions. While these tests have proven valuable, the Northwestern Medicine study highlights their inherent limitations in fully capturing an individual’s true cardiovascular risk profile.
Why ApoB Emerges as a More Potent Indicator of Cardiovascular Risk
"Research has consistently shown that apolipoprotein B (apoB) is a more effective tool for identifying individuals at risk because it quantifies the total number of harmful cholesterol-carrying particles circulating in the blood," explained Dr. Kohli-Lynch.
Unlike conventional cholesterol tests that measure the amount of cholesterol within various lipoprotein particles, apoB directly measures the number of these specific particles themselves. These apoB-containing particles, which include LDL, very-low-density lipoprotein (VLDL), and intermediate-density lipoprotein (IDL), are considered atherogenic – meaning they are capable of contributing to the development of arterial plaque. By counting these particles, apoB provides a more direct and precise assessment of the cumulative burden of atherogenic lipoproteins, offering a clearer picture of an individual’s susceptibility to cardiovascular disease.
Despite the growing body of scientific evidence supporting the superiority of apoB, its adoption into routine clinical practice has been slow. A primary barrier, according to Dr. Kohli-Lynch, has been the perceived inconvenience and additional cost associated with an extra blood draw beyond the standard lipid panel.
"Our study was designed to rigorously answer a critical question: Is the additional expenditure for using apoB to guide treatment intensification justifiable when compared to relying on LDL measurements?" Dr. Kohli-Lynch elaborated.
A Comprehensive Computer Model Illuminates Testing Strategy Effectiveness
To address this pivotal question, the research team employed a sophisticated computer simulation model. This model was designed to represent a cohort of 250,000 U.S. adults who were deemed eligible for statin therapy but had not yet been diagnosed with cardiovascular disease. This demographic represents a crucial population for primary prevention efforts.
The simulation meticulously compared three distinct strategies for guiding cholesterol-lowering treatment:
- Strategy 1: LDL-C Goals: This approach adhered to traditional guidelines, focusing on achieving target LDL cholesterol levels.
- Strategy 2: Non-HDL-C Goals: This strategy utilized non-HDL cholesterol as the primary target for treatment decisions. Non-HDL cholesterol is calculated by subtracting HDL cholesterol from total cholesterol and is considered a broader measure of atherogenic lipoproteins.
- Strategy 3: ApoB Goals: This innovative approach centered on achieving target apoB levels.
Within each simulated scenario, when patients failed to meet their assigned cholesterol target, treatment intensification was systematically implemented. This typically involved escalating the dosage of statins or switching to more potent statin medications. If the therapeutic goals remained unmet, the next step involved adding other cholesterol-lowering medications, such as ezetimibe, a cholesterol absorption inhibitor.
The researchers meticulously tracked each simulated strategy over the course of a lifetime, projecting key health outcomes. These projections included the incidence of heart attacks and strokes, overall life expectancy, quality-adjusted life years (a measure that accounts for both the length and quality of life), and cumulative healthcare costs associated with managing cardiovascular disease.
The results of this extensive simulation were unequivocal. The strategy that guided treatment intensification based on apoB levels consistently outperformed both the LDL-C and non-HDL-C approaches. This superior performance manifested in several critical areas: improved overall health outcomes, a greater number of prevented cardiovascular events, and a cost-effectiveness profile that the researchers deemed highly favorable for the U.S. healthcare system.
Evolving Cholesterol Guidelines Underscore the Imperative for Accurate Testing
These findings arrive at a pivotal moment in cardiovascular medicine. The therapeutic landscape for cholesterol management has expanded dramatically, with an increasing array of effective cholesterol-lowering medications now available to clinicians. Furthermore, earlier this year, the American Heart Association, in conjunction with ten other leading medical organizations, released updated guidelines. These updated recommendations advocate for initiating cholesterol-lowering therapy at younger ages for a broader segment of the population, reflecting a more proactive approach to cardiovascular risk reduction.
"The implications of these new guidelines are profound," noted Dr. Kohli-Lynch. "As we are now encouraging more individuals to begin cholesterol-lowering therapy at earlier stages of life and potentially for longer durations, it becomes increasingly critical to accurately identify precisely who would derive the most significant benefit from intensive treatment. Our research strongly suggests that apoB testing is the key to achieving this precision."
The study also acknowledged the contributions of other Northwestern coauthors, including Drs. John Wilkins and Samuel Luebbe. The research was generously supported by the American Heart Association Career Development Award 24CDA1274989, awarded to Dr. Kohli-Lynch, underscoring the significance and potential impact of this line of inquiry.
Broader Implications for Public Health and Healthcare Economics
The implications of this Northwestern Medicine study extend far beyond the immediate clinical decisions regarding individual patient care. The potential to prevent more heart attacks and strokes through more precise risk stratification carries immense public health benefits, not only in terms of lives saved and improved quality of life but also in reducing the substantial economic burden associated with managing these debilitating conditions.
Economic Analysis and Value Proposition:
The cost-effectiveness analysis presented in the study is particularly noteworthy. While an apoB test might incur a slightly higher upfront cost than a standard LDL test, the simulation demonstrated that the long-term savings generated by preventing more cardiovascular events—such as hospitalizations for heart attacks, stroke rehabilitation, and ongoing management of chronic conditions—far outweigh this initial investment. This represents a compelling value proposition for healthcare payers, including insurance companies and government programs like Medicare and Medicaid.
Potential for Guideline Revisions:
Given the robust evidence presented, it is plausible that future revisions to cardiovascular guidelines will increasingly incorporate apoB measurements as a standard component of lipid assessment, particularly for high-risk individuals or those with borderline results on traditional tests. This would necessitate a shift in laboratory practices and physician education to facilitate broader adoption.
Addressing Health Disparities:
While not explicitly detailed in the original summary, more precise risk assessment tools like apoB could potentially play a role in addressing health disparities. If certain populations are found to have a higher prevalence of atherogenic particles despite seemingly "normal" LDL levels, identifying them through apoB could lead to earlier and more effective interventions, helping to mitigate disparities in cardiovascular disease outcomes.
The Evolving Science of Lipidology:
This research aligns with a broader trend in lipidology, moving beyond simply measuring cholesterol levels to understanding the particle number and size of lipoproteins. The concept that the number of atherogenic particles, rather than just the cholesterol content within them, is a more direct driver of atherosclerosis is gaining significant traction within the scientific community.
Challenges to Implementation:
Despite the compelling evidence, the path to widespread adoption of apoB testing will likely involve overcoming several hurdles. These include:
- Physician Education and Awareness: Ensuring that healthcare providers are fully aware of the benefits and appropriate use of apoB testing.
- Laboratory Infrastructure: Adapting laboratory workflows and ensuring availability of apoB testing across diverse healthcare settings.
- Insurance Coverage: Advocating for consistent and comprehensive insurance coverage for apoB testing.
- Patient Understanding: Educating patients about the significance of apoB and its role in their cardiovascular health.
Conclusion:
The Northwestern Medicine study published in JAMA represents a significant advancement in the field of cardiovascular risk assessment. By demonstrating the superior clinical utility and cost-effectiveness of apolipoprotein B (apoB) testing in guiding cholesterol-lowering therapy, this research offers a compelling case for its broader integration into routine clinical practice. As the medical community continues to refine strategies for preventing heart disease and stroke, embracing more precise diagnostic tools like apoB promises to unlock substantial improvements in patient outcomes and enhance the efficiency of healthcare resource allocation. The journey from research to widespread clinical adoption is often complex, but the potential benefits of this evidence-based approach are too significant to ignore, paving the way for a future where cardiovascular disease prevention is more targeted, effective, and ultimately, more life-saving.
