
 By Gilang Cahya
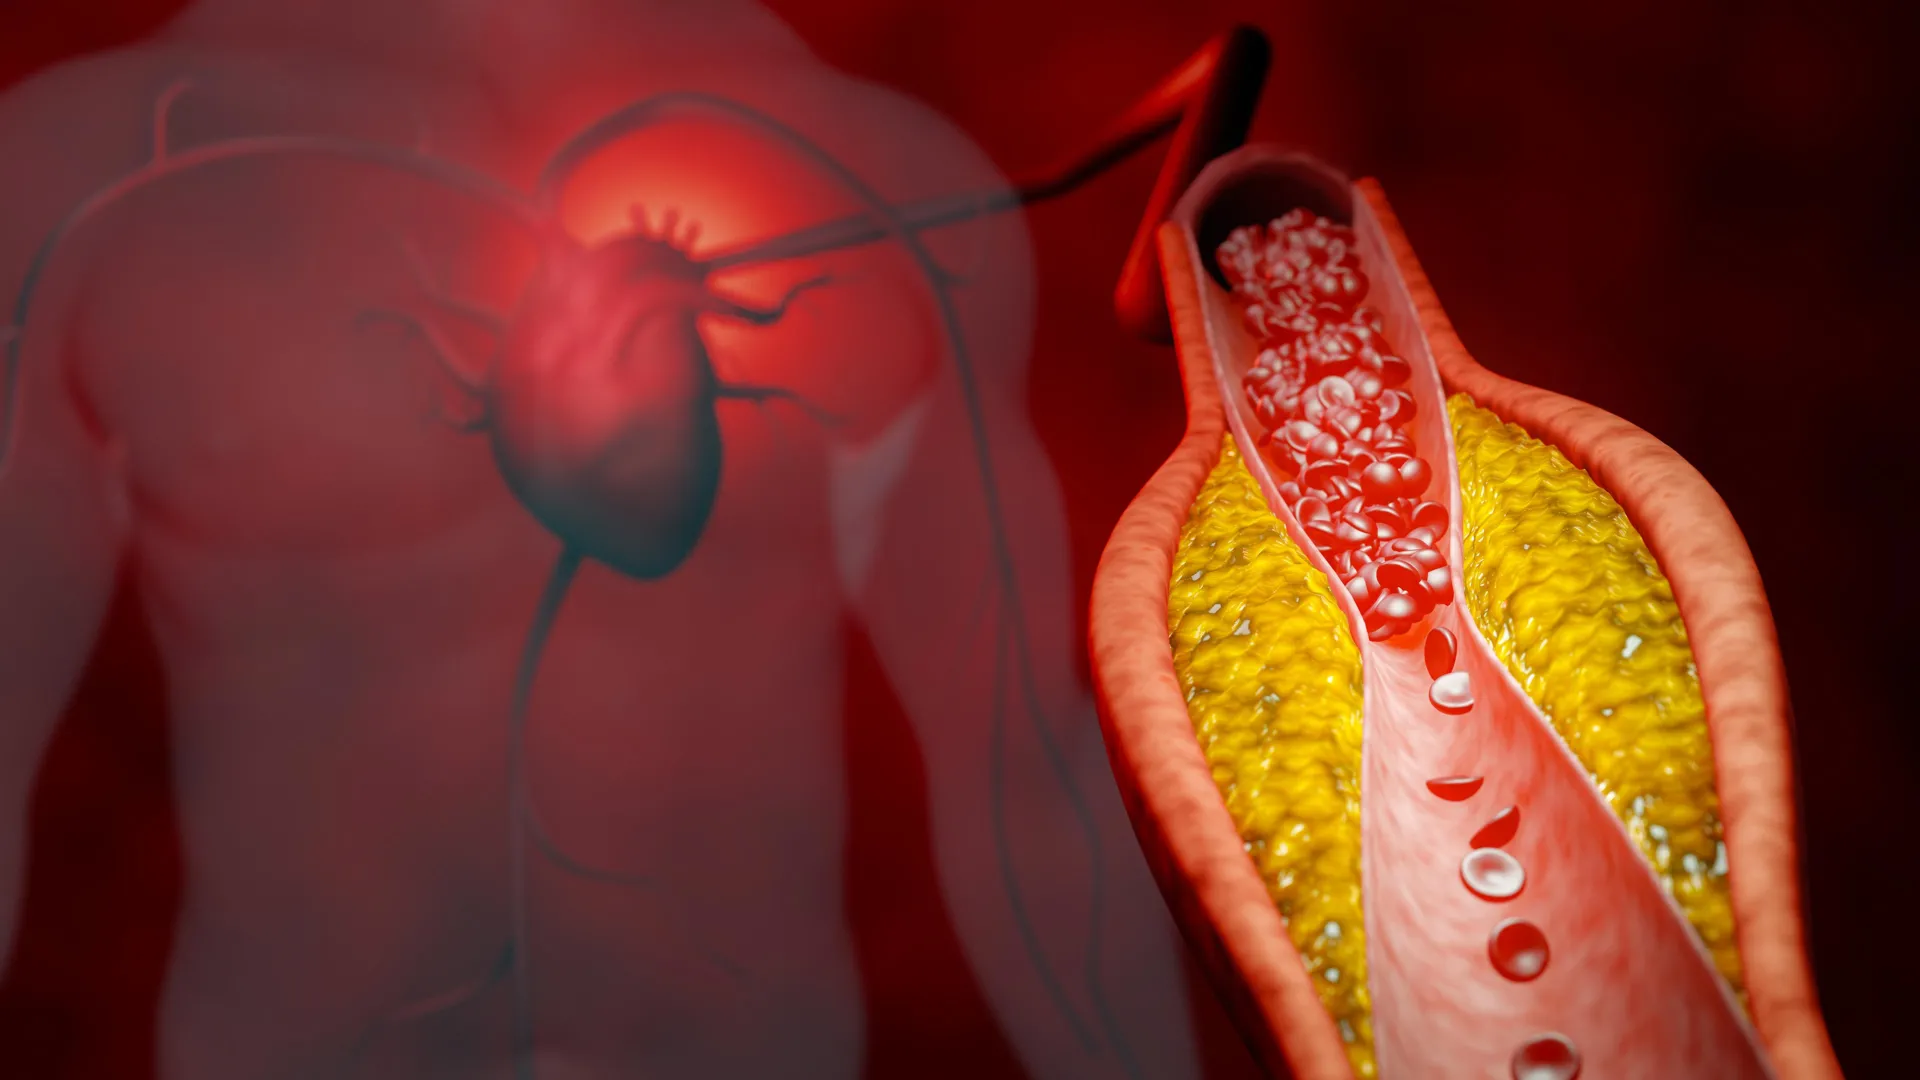
Millions of Americans undergo annual blood tests to monitor their low-density lipoprotein (LDL) cholesterol, commonly referred to as "bad" cholesterol. However, groundbreaking new research from Northwestern Medicine suggests that an alternative blood test, measuring apolipoprotein B (apoB), may offer a more precise and effective method for identifying individuals who require more aggressive treatment to mitigate the risk of heart attacks and strokes. The study, published in the prestigious JAMA, indicates that apoB testing surpasses LDL and non-high-density lipoprotein (non-HDL) cholesterol in guiding decisions to intensify cholesterol-lowering therapies, including statins and other pharmacological interventions.
This comprehensive analysis represents the first to demonstrate that using apoB levels to direct cholesterol treatment not only improves health outcomes but also proves to be a cost-effective strategy for U.S. healthcare payers. "We found that apoB testing to intensify cholesterol-lowering medication would prevent more heart attacks and strokes than current practice, and that these health benefits were achieved at a cost that represents good value for U.S. healthcare payers," stated Ciaran Kohli-Lynch, the study’s lead author and an assistant professor of preventive medicine in the division of epidemiology at Northwestern University Feinberg School of Medicine. This finding is particularly significant given that heart disease remains the leading cause of death in the United States, contributing to substantial healthcare expenditures.
Understanding the Role of Cholesterol in Cardiovascular Disease
The accumulation of cholesterol within artery walls is a well-established pathway leading to cardiovascular events. Over time, tiny cholesterol-carrying particles can become lodged in the inner lining of arteries. These particles contribute to the formation of plaques, which progressively narrow and harden the arteries, restricting blood flow. This compromised blood flow significantly elevates the risk of life-threatening events such as heart attacks and strokes.
For decades, clinicians have relied on LDL cholesterol and non-HDL cholesterol levels as primary indicators for initiating or intensifying cholesterol-lowering treatments. While these conventional tests provide valuable insights into a patient’s lipid profile, they do not always offer a complete picture of an individual’s overall cardiovascular risk.
Apolipoprotein B: A More Direct Measure of Risk
The Northwestern Medicine study highlights the superior predictive power of apoB. "Research strongly shows that apolipoprotein B (apoB) is better at identifying who is at risk, because it counts the total number of harmful particles in the blood," explained Kohli-Lynch. Unlike standard cholesterol tests that measure the amount of cholesterol, apoB quantifies the number of particles that carry cholesterol, particularly those implicated in plaque formation. This direct measurement of atherogenic particles makes apoB a more precise indicator of cardiovascular risk.
Atherogenic particles are those that can contribute to the buildup of plaque in the arteries. These include LDL particles, but also other types of lipoproteins that can be detrimental to cardiovascular health. By counting the total number of these potentially harmful particles, apoB offers a more comprehensive assessment of the underlying process driving atherosclerosis.
Despite the growing body of evidence supporting apoB’s utility, its widespread adoption in routine clinical practice has been slow. One significant barrier has been the perception of increased cost and inconvenience, as measuring apoB often requires a separate blood draw in addition to the standard lipid panel. "Our study asked: Is it worth spending extra money to use apoB instead of LDL to guide treatment intensification?" Kohli-Lynch noted, framing the central question addressed by their research.
A Comprehensive Simulation of Cholesterol Testing Strategies
To rigorously evaluate the cost-effectiveness of apoB testing, the research team employed a sophisticated computer simulation. This model was designed to represent a hypothetical cohort of 250,000 U.S. adults who were candidates for statin therapy but had no pre-existing cardiovascular disease. This demographic was chosen because it represents a crucial population for primary prevention efforts.
The simulation meticulously compared three distinct strategies for guiding cholesterol-lowering treatment:
- LDL-C Guided Strategy: This approach adhered to current standard practice, where treatment intensification was based on achieving target LDL cholesterol levels.
- Non-HDL-C Guided Strategy: This strategy utilized non-HDL cholesterol levels as the primary metric for treatment decisions. Non-HDL cholesterol is calculated by subtracting HDL cholesterol from total cholesterol and is considered a broader measure of atherogenic lipoproteins.
- ApoB Guided Strategy: This novel approach focused on targeting apoB levels, aiming to reduce the number of atherogenic particles.
Within each simulated strategy, when patients failed to meet their designated lipid-lowering targets, their treatment regimen was incrementally intensified. This typically involved escalating to more potent statin medications. If further improvement was still necessary, other classes of lipid-lowering drugs, such as ezetimibe, were introduced.
The researchers followed each of these simulated treatment pathways over the entire lifespan of the individuals in the cohort. During this extended follow-up period, they meticulously estimated the incidence of heart attacks and strokes, projected life expectancy, assessed quality of life adjustments, and calculated the associated healthcare costs for each strategy.
Superior Outcomes and Cost-Effectiveness
The results of the simulation were compelling. The strategy guided by apoB consistently outperformed both the LDL-C and non-HDL-C approaches. It demonstrated a significant improvement in overall health outcomes, leading to a greater number of prevented cardiovascular events, including heart attacks and strokes. Crucially, these enhanced health benefits were achieved at a cost that the researchers deemed cost-effective, representing a favorable return on investment for the U.S. healthcare system.
The simulation projected that adopting apoB-guided therapy could avert a substantial number of cardiovascular events annually. For instance, if this strategy were implemented nationwide for the relevant patient population, it could potentially prevent tens of thousands of heart attacks and strokes each year, thereby saving lives and reducing long-term healthcare burdens associated with managing these debilitating conditions.
Evolving Cholesterol Guidelines and the Need for Precision
The timing of these findings is particularly relevant given the recent evolution of cardiovascular guidelines. Earlier this year, the American Heart Association, in conjunction with ten other leading medical organizations, released updated guidelines recommending that a broader segment of the population, including many individuals at younger ages, should initiate cholesterol-lowering therapy. This shift underscores the growing emphasis on early and effective intervention to prevent cardiovascular disease.
"This means it is increasingly important to accurately identify who would benefit most from intensive treatment," stated Kohli-Lynch. As more individuals become candidates for lipid-lowering therapy, the ability to precisely identify those at highest risk and most likely to benefit from aggressive treatment becomes paramount. ApoB testing offers a tool to achieve this precision, potentially averting unnecessary treatment for some while ensuring optimal care for those who need it most.
Broader Implications and Future Directions
The implications of this research extend beyond clinical practice. For healthcare payers, the demonstrated cost-effectiveness of apoB-guided therapy suggests a pathway to optimize resource allocation and improve population health. By preventing costly cardiovascular events, the healthcare system could see significant long-term savings.
Furthermore, the study may spur greater adoption of apoB testing by primary care physicians and cardiologists. Increased awareness of its superior predictive power and cost-effectiveness could lead to its integration into routine lipid management protocols. This could involve changes in laboratory testing practices and physician education initiatives.
The Northwestern Medicine study team, including Drs. John Wilkins and Samuel Luebbe, who also contributed as coauthors, has laid a strong foundation for future research. Further investigations could explore the long-term adherence to apoB-guided therapy, its impact on different demographic subgroups, and its role in managing patients with familial hypercholesterolemia or other genetic lipid disorders.
The study, titled "Cost-Effectiveness of ApoB, Non-HDL-C, and LDL-C Goals for Primary Prevention Lipid-Lowering Therapy," was supported by the American Heart Association Career Development Award 24CDA1274989 (Dr. Kohli-Lynch). This research not only provides compelling evidence for a more effective approach to cardiovascular risk management but also signals a potential paradigm shift in how cholesterol is assessed and managed in the United States, ultimately aiming to reduce the burden of heart disease and stroke on individuals and the healthcare system alike.
