
 By Gilang Cahya
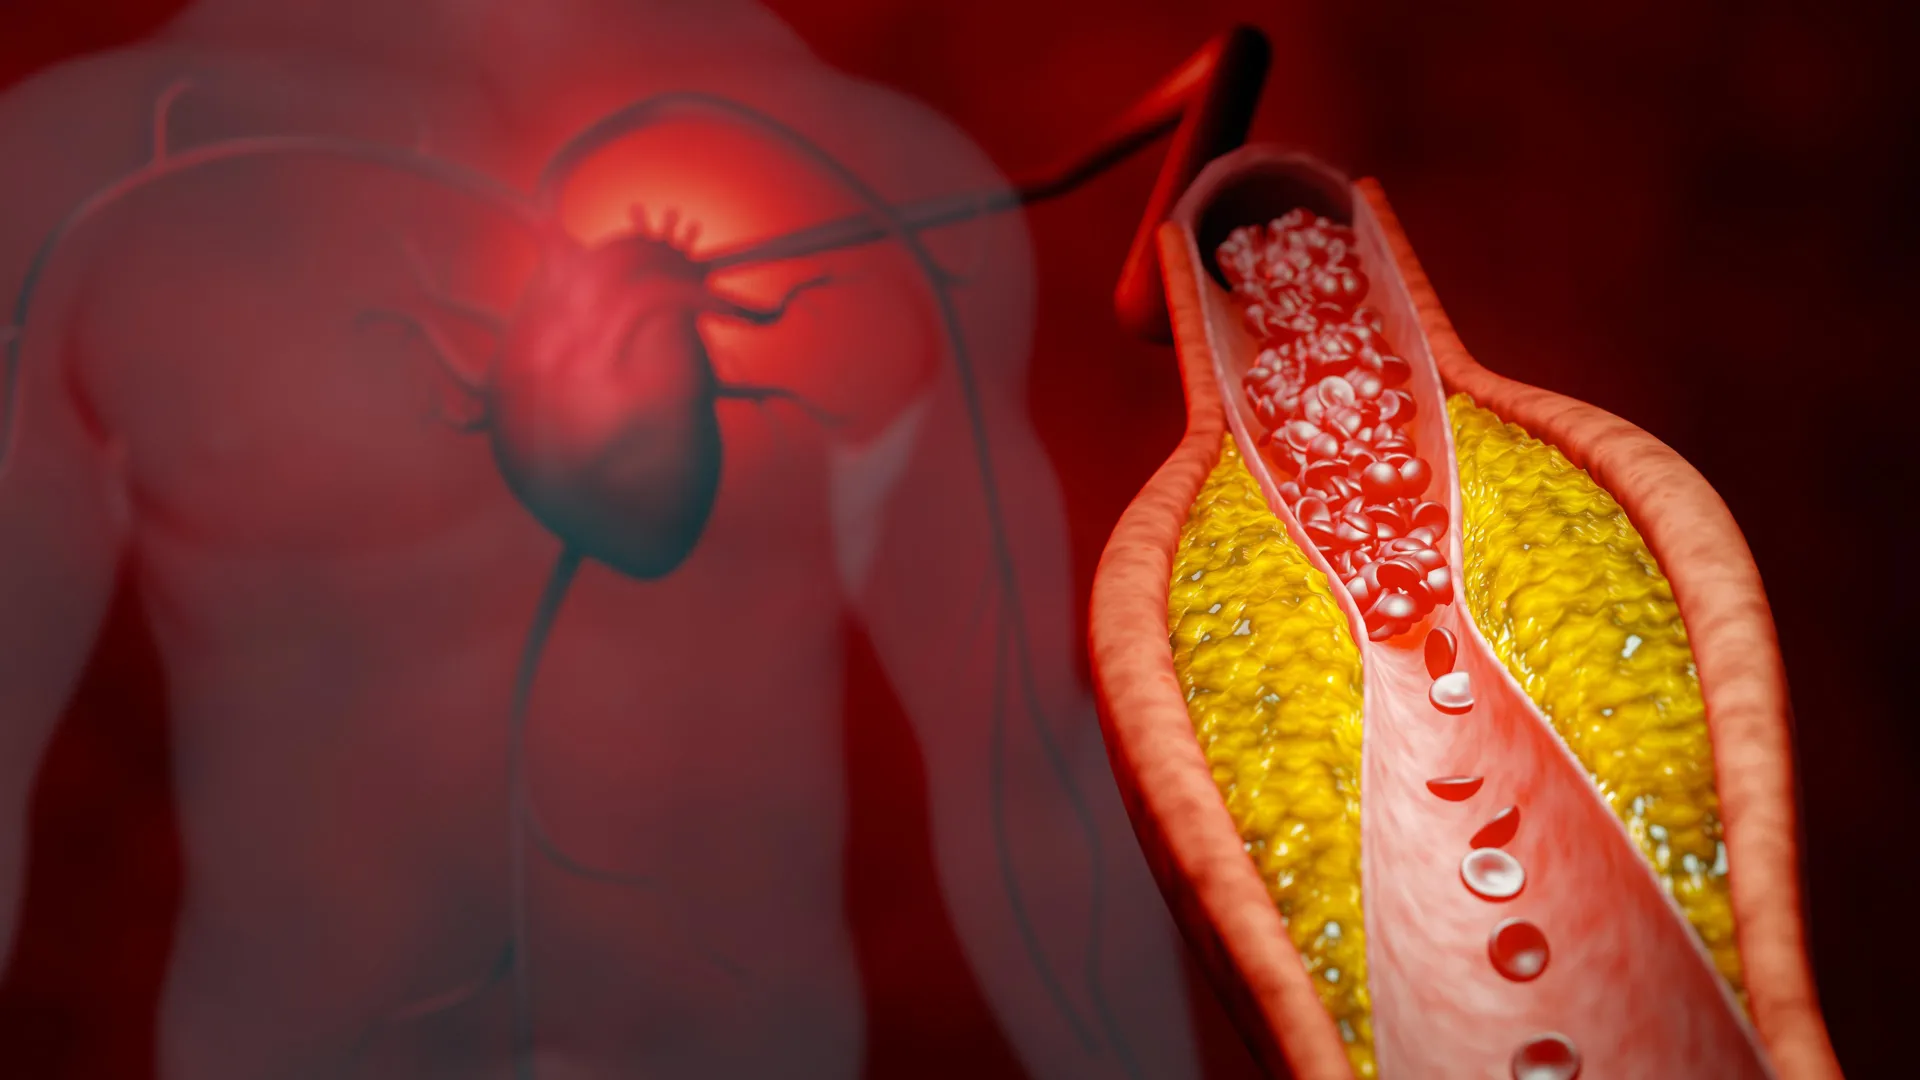
Millions of Americans undergo annual blood tests to monitor their low-density lipoprotein (LDL) cholesterol, commonly referred to as "bad" cholesterol. However, groundbreaking research originating from Northwestern Medicine indicates that an alternative test, apolipoprotein B (apoB), may provide a more precise identification of individuals who would benefit from more aggressive treatment strategies to mitigate the risks of heart attacks and strokes. This pivotal study, published in the esteemed journal JAMA, suggests a significant shift in how cardiovascular risk is assessed and managed within the U.S. healthcare system.
Unveiling the Superiority of ApoB Testing
The Northwestern Medicine study revealed that measuring apolipoprotein B (apoB) demonstrated superior efficacy compared to tracking LDL or non-high-density lipoprotein (non-HDL) cholesterol levels when determining the necessity of intensifying cholesterol-lowering therapies, which include statins and other pharmacological interventions. This finding carries profound implications for clinical practice, potentially leading to a more proactive and effective approach to preventing cardiovascular events.
Dr. Ciaran Kohli-Lynch, the lead author of the study and an assistant professor of preventive medicine in the division of epidemiology at Northwestern University Feinberg School of Medicine, articulated the study’s key findings: "We found that apoB testing to intensify cholesterol-lowering medication would prevent more heart attacks and strokes than current practice, and that these health benefits were achieved at a cost that represents good value for U.S. healthcare payers." This statement underscores not only the clinical advantage but also the economic feasibility of adopting apoB testing.
Dr. Kohli-Lynch further emphasized the novelty of their research, noting, "This is the first comprehensive analysis to show that using apoB to guide cholesterol treatment is also cost effective." This comprehensive economic analysis is crucial, as healthcare systems often face budgetary constraints, and the adoption of new diagnostic tools necessitates a clear demonstration of value.
The Pervasive Threat of Heart Disease in the United States
Heart disease continues to hold its grim position as the leading cause of death in the United States, exacting a heavy toll on both public health and national healthcare expenditure. The insidious nature of cardiovascular disease lies in the gradual accumulation of cholesterol-laden particles within arterial walls. Over time, these particles can become lodged, forming plaques that progressively narrow arteries, impede blood flow, and significantly elevate the risk of catastrophic events such as heart attacks and strokes. According to the Centers for Disease Control and Prevention (CDC), approximately one in every five deaths in the U.S. is attributed to heart disease, highlighting the urgent need for more effective preventive measures. The annual economic burden of heart disease and stroke in the U.S. is estimated to be over $200 billion, encompassing direct medical costs and lost productivity.
Beyond LDL: Why ApoB Emerges as a More Potent Risk Indicator
For decades, healthcare professionals have relied on LDL cholesterol and non-HDL cholesterol levels as primary metrics for guiding decisions regarding the initiation or intensification of cholesterol-lowering treatments. While these conventional tests provide valuable insights into a patient’s lipid profile, they do not always offer a complete picture of an individual’s unique cardiovascular risk.
Dr. Kohli-Lynch explained the underlying mechanism of apoB’s superiority: "Research strongly shows that apolipoprotein B (apoB) is better at identifying who is at risk, because it counts the total number of harmful particles in the blood." Unlike standard cholesterol tests that measure the amount of cholesterol within particles, apoB directly quantifies the number of apolipoprotein B-containing particles. These are precisely the particles that are atherogenic, meaning they contribute to the formation of atherosclerotic plaques. Each apoB particle, regardless of its cholesterol content, has the potential to infiltrate artery walls and contribute to plaque buildup. Therefore, a higher number of apoB particles directly correlates with a greater risk of cardiovascular events.
This distinction is critical. A person might have a "normal" LDL cholesterol level, but if they have a high number of apoB particles, their risk of heart disease could still be significantly elevated. Conversely, someone with a slightly elevated LDL might have a lower risk if their apoB count is within a healthier range. This nuance underscores why apoB offers a more direct and accurate measure of the underlying pathological process driving cardiovascular disease.
Bridging the Gap: The Challenge of ApoB Adoption
Despite the accumulating scientific evidence supporting the clinical utility of apoB, its widespread adoption in routine patient care has been a gradual process. A primary obstacle has been the logistical and financial considerations associated with the test. Measuring apoB typically necessitates an additional blood draw beyond the standard lipid panel, which can increase both the cost and the inconvenience for patients and healthcare providers.
Dr. Kohli-Lynch candidly addressed this concern: "Our study asked: Is it worth spending extra money to use apoB instead of LDL to guide treatment intensification?" This question lies at the heart of the research’s practical application, seeking to quantify the return on investment in terms of improved health outcomes and cost savings.
A Sophisticated Simulation: Comparing Cholesterol Testing Strategies
To rigorously answer the question of apoB’s cost-effectiveness, the research team employed a sophisticated computer simulation. This model was designed to represent a large cohort of 250,000 U.S. adults who were deemed eligible for statin therapy but had not yet developed established cardiovascular disease. This demographic is crucial as it represents the primary prevention population, where early and accurate risk assessment can have the greatest impact.
The simulation meticulously compared three distinct approaches to guiding cholesterol management:
- Strategy 1: LDL-C Goals: This approach adhered to current standard practice, where treatment intensification was guided by whether a patient’s LDL cholesterol levels met predefined target ranges.
- Strategy 2: Non-HDL-C Goals: This strategy utilized non-HDL cholesterol levels as the primary metric for treatment adjustments. Non-HDL cholesterol is calculated by subtracting HDL cholesterol from total cholesterol and is considered by some to be a more comprehensive measure than LDL alone, as it includes other potentially harmful cholesterol-carrying particles.
- Strategy 3: ApoB Goals: This approach employed apolipoprotein B levels as the guiding factor for treatment intensification.
In each simulated scenario, when patients failed to achieve their specified cholesterol targets based on the respective metric, treatment was escalated. This escalation typically involved transitioning to more potent statin medications. If further improvement was still needed, ezetimibe, a cholesterol absorption inhibitor, was introduced as a subsequent step.
The research team followed each of these simulated strategies over the entire lifetime of the individuals represented in the model. During this extended follow-up period, the simulation meticulously estimated critical health outcomes, including the incidence of heart attacks and strokes, overall life expectancy, quality of life adjusted for health status, and the cumulative healthcare costs associated with each strategy.
The findings from this extensive simulation were compelling. The strategy that utilized apoB levels to guide treatment consistently outperformed both the LDL and non-HDL cholesterol-guided approaches. It not only led to improved overall health outcomes but also demonstrated a greater capacity to prevent cardiovascular events. Crucially, these superior health benefits were achieved in a manner that the researchers deemed cost-effective, validating the initial hypothesis that the added expense of apoB testing is offset by significant long-term savings in healthcare and improved patient well-being.
Evolving Guidelines and the Imperative for Precision
The timing of these findings is particularly significant, coinciding with a period of substantial evolution in cardiovascular disease management. The availability of novel and more potent cholesterol-lowering medications has expanded the therapeutic arsenal for clinicians. Furthermore, earlier this year, the American Heart Association, in conjunction with ten other prominent medical organizations, released updated guidelines. These updated recommendations advocate for initiating cholesterol-lowering therapy at younger ages for a broader segment of the population, reflecting a more aggressive stance on primary prevention.
"This means it is increasingly important to accurately identify who would benefit most from intensive treatment," Dr. Kohli-Lynch stated, highlighting the direct link between the new guidelines and the necessity for precise risk assessment tools like apoB testing. As more individuals are recommended for treatment, the ability to differentiate those at highest risk becomes paramount to optimize resource allocation and maximize the impact of interventions.
Broader Implications and Future Directions
The implications of this research extend beyond the immediate clinical decision-making process. Widespread adoption of apoB testing could lead to a paradigm shift in how cardiovascular risk is perceived and managed. It may empower both patients and physicians with a clearer, more actionable understanding of individual risk.
The study also opens avenues for further research. Future investigations could explore the optimal apoB thresholds for different patient populations, refine cost-effectiveness models based on real-world data, and examine the impact of apoB-guided therapy on specific subgroups, such as individuals with diabetes or those with a family history of premature heart disease.
The cost-effectiveness analysis, in particular, will be crucial for informing policy decisions by healthcare payers and professional organizations. If the data strongly supports apoB as a superior and cost-effective tool, it could pave the way for its inclusion in routine clinical guidelines and insurance coverage.
The Northwestern coauthors of this significant study include Dr. John Wilkins and Dr. Samuel Luebbe. The research was supported by the American Heart Association Career Development Award 24CDA1274989, granted to Dr. Kohli-Lynch, underscoring the commitment of leading cardiovascular organizations to advancing research in this critical area.
In conclusion, the Northwestern Medicine study offers compelling evidence that apolipoprotein B testing is not only a more accurate indicator of cardiovascular risk than traditional LDL and non-HDL cholesterol measurements but also a cost-effective strategy for guiding treatment intensification. As the landscape of cardiovascular disease prevention continues to evolve, embracing such advanced diagnostic tools will be essential in the ongoing fight against the nation’s leading cause of death. The findings represent a significant step forward in personalized medicine, promising to save lives and reduce the burden of heart disease in the United States.
