
 By Gilang Cahya
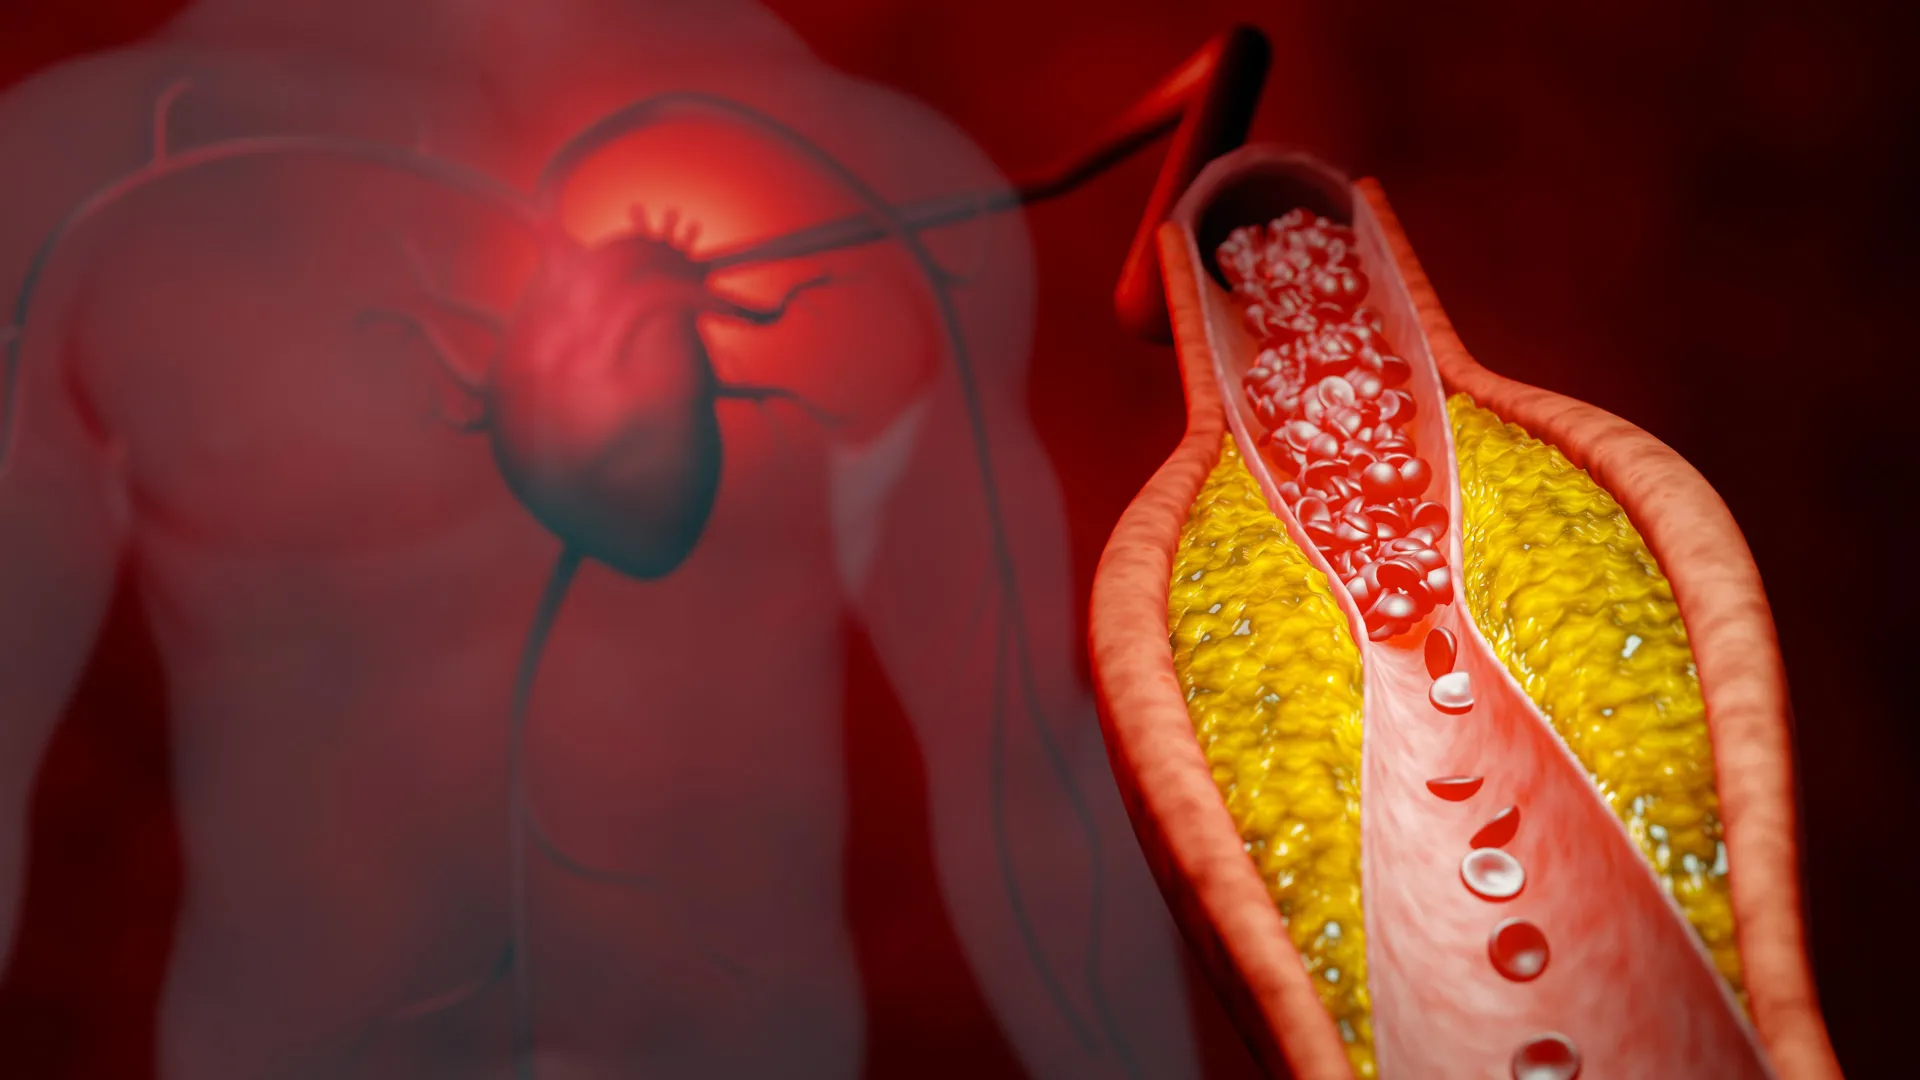
Millions of Americans undergo annual blood tests to measure their low-density lipoprotein (LDL) cholesterol, commonly referred to as "bad" cholesterol. This ubiquitous test has been a cornerstone of cardiovascular risk assessment for decades, guiding therapeutic decisions aimed at preventing heart attacks and strokes. However, groundbreaking new research emerging from Northwestern Medicine indicates that a different biomarker, apolipoprotein B (apoB), may offer a more precise and effective method for identifying individuals who would benefit from more aggressive cholesterol-lowering interventions. The study, published in the prestigious journal JAMA, suggests that prioritizing apoB measurement could lead to a significant reduction in cardiovascular events and represent a cost-effective strategy for the U.S. healthcare system.
A More Direct Measure of Harmful Cholesterol Particles
The core finding of the Northwestern Medicine study, led by Assistant Professor of Preventive Medicine Ciaran Kohli-Lynch at the Northwestern University Feinberg School of Medicine, is that measuring apolipoprotein B (apoB) proved more effective than tracking LDL or non-HDL cholesterol when determining the need to intensify cholesterol-lowering therapies, including statins and other prescribed medications. This is particularly significant given that heart disease remains the leading cause of death in the United States, contributing to an immense burden on healthcare resources and profoundly impacting the lives of countless individuals and families.
The mechanism by which cholesterol contributes to cardiovascular disease is well-established: over time, small cholesterol-carrying particles can accumulate within the walls of arteries. This buildup forms plaques, which can narrow the arteries, restrict blood flow, and ultimately trigger heart attacks and strokes. While LDL and non-HDL cholesterol tests provide valuable insights, they do not fully encapsulate the complex picture of an individual’s cardiovascular risk.
"We found that apoB testing to intensify cholesterol-lowering medication would prevent more heart attacks and strokes than current practice, and that these health benefits were achieved at a cost that represents good value for U.S. healthcare payers," stated Dr. Kohli-Lynch, emphasizing the dual benefit of improved health outcomes and economic efficiency. He further highlighted that this represents the first comprehensive analysis demonstrating the cost-effectiveness of using apoB to guide cholesterol treatment.
The advantage of apoB lies in its direct measurement of the number of cholesterol-carrying particles circulating in the blood that are capable of contributing to plaque formation. Unlike standard cholesterol tests that measure the amount of cholesterol contained within these particles, apoB quantifies the actual number of these potentially harmful lipoproteins. This distinction is critical because a higher number of these particles, regardless of the precise cholesterol content within each, directly correlates with increased arterial wall penetration and subsequent plaque development.
"Research strongly shows that apolipoprotein B (apoB) is better at identifying who is at risk, because it counts the total number of harmful particles in the blood," explained Dr. Kohli-Lynch. This direct count makes apoB a more precise indicator of the underlying atherogenic process, the biological pathway that leads to the buildup of plaques in arteries.
The Historical Context of Cholesterol Testing
For decades, LDL cholesterol has been the primary target for managing dyslipidemia. The rationale behind this focus was that high LDL levels were strongly associated with increased cardiovascular risk. Non-HDL cholesterol, which includes LDL and other atherogenic lipoproteins like very-low-density lipoprotein (VLDL) and intermediate-density lipoprotein (IDL), was later introduced as a complementary measure, providing a broader assessment of "bad" cholesterol. These tests have undoubtedly played a crucial role in preventing a vast number of cardiovascular events.
However, as medical understanding has evolved and diagnostic technologies have advanced, it has become apparent that these established markers may not capture the full spectrum of risk for all individuals. Some patients with seemingly "normal" LDL levels can still experience cardiovascular events, while others with elevated LDL may not develop significant disease. This variability has prompted researchers to explore alternative or supplementary biomarkers that could offer a more refined risk stratification.
Apolipoprotein B has been recognized by researchers for some time as a potentially superior marker. Its ability to count the number of atherogenic particles offers a more direct proxy for the underlying biological process of atherosclerosis. Despite this growing body of evidence, apoB testing has not yet become a routine component of standard cardiovascular risk assessment in clinical practice.
Barriers to Widespread Adoption
One significant factor contributing to the slower adoption of apoB testing is the practical aspect of its measurement. Currently, measuring apoB typically requires a separate blood draw in addition to the standard lipid panel that includes LDL and HDL. This can lead to increased costs for both patients and healthcare providers, as well as an added layer of inconvenience for individuals undergoing blood tests.
"Our study asked: Is it worth spending extra money to use apoB instead of LDL to guide treatment intensification?" Dr. Kohli-Lynch articulated the central question the research aimed to address, underscoring the economic considerations that influence clinical practice. The findings suggest that the benefits derived from more accurate risk identification and targeted treatment intensification outweigh the incremental costs associated with apoB testing.
Methodology: A Lifetime Simulation of Treatment Strategies
To rigorously assess the comparative effectiveness and cost-effectiveness of different cholesterol testing strategies, the Northwestern Medicine research team employed a sophisticated computer simulation. This model was designed to represent a large cohort of 250,000 U.S. adults who were deemed eligible for statin therapy but did not have pre-existing cardiovascular disease. This population selection is crucial as it focuses on primary prevention, the stage where early and accurate risk identification is paramount.
The simulation meticulously compared three distinct approaches to guiding cholesterol-lowering treatment:
- LDL-C Goals: This approach followed current standard practice, where treatment intensification is guided by achieving specific target levels for LDL cholesterol.
- Non-HDL-C Goals: This strategy utilized non-HDL cholesterol levels as the primary metric for treatment decisions, representing another commonly used approach.
- ApoB Goals: This approach prioritized apoB levels, aiming to achieve specific target concentrations of this biomarker.
Within each of these simulated strategies, the researchers modeled a stepwise intensification of treatment. When a patient in the simulation failed to meet their assigned lipid target (whether LDL, non-HDL, or apoB), their treatment regimen would be escalated. This escalation would first involve transitioning to a more potent statin medication. If further improvement was still needed, the simulation would then introduce ezetimibe, a medication that works by inhibiting cholesterol absorption in the intestine, as an add-on therapy.
The researchers then tracked the simulated patients over their entire lifetimes. During this extended follow-up period, they meticulously estimated a range of critical health outcomes and economic factors, including the incidence of heart attacks, strokes, overall life expectancy, quality-adjusted life years (a measure that accounts for both the length and quality of life), and the cumulative healthcare costs associated with each treatment strategy.
Compelling Results: ApoB Emerges as the Superior Strategy
The results of this comprehensive simulation were unequivocal. The strategy that utilized apoB to guide treatment consistently outperformed both the LDL and non-HDL cholesterol-guided approaches across all measured parameters. The apoB-guided strategy not only led to improved overall health outcomes but also demonstrably prevented a greater number of cardiovascular events, such as heart attacks and strokes. Crucially, these superior health benefits were achieved in a manner that the researchers determined to be cost-effective, meaning that the additional investment in apoB testing and subsequent treatment adjustments provided a favorable return in terms of reduced healthcare utilization and improved population health.
This finding has significant implications for how cardiovascular risk is assessed and managed in the United States. The current healthcare landscape is characterized by a substantial burden of cardiovascular disease, which accounts for a significant portion of annual healthcare expenditures. By identifying individuals who are at higher risk more accurately and intervening earlier with more effective treatments, the healthcare system could potentially avert costly emergency interventions and long-term chronic care needs associated with heart attacks and strokes.
Evolving Guidelines and the Imperative for Precision
The findings of this study arrive at a pivotal moment in cardiovascular medicine. The landscape of available cholesterol-lowering medications has expanded dramatically in recent years, offering clinicians a more diverse and potent arsenal to combat dyslipidemia. Earlier in 2023, the American Heart Association, in conjunction with 10 other leading medical organizations, released updated guidelines that recommend initiating cholesterol-lowering therapy at younger ages for a broader segment of the population.
These updated guidelines, which reflect a growing understanding of the long-term cumulative risk associated with elevated cholesterol, underscore the increasing importance of accurately identifying which individuals stand to benefit the most from intensive treatment. The ability to precisely pinpoint those at highest risk is essential to avoid overtreatment of lower-risk individuals while ensuring that those who would derive the greatest benefit from aggressive therapy do not miss out.
"This means it is increasingly important to accurately identify who would benefit most from intensive treatment," Dr. Kohli-Lynch reiterated, highlighting the direct link between evolving clinical guidelines and the need for more precise diagnostic tools. The apoB test, according to this research, may be that crucial tool.
Broader Implications for Public Health and Healthcare Economics
The implications of this research extend beyond individual patient care. If apoB testing becomes more widely adopted and integrated into routine clinical practice, it could lead to a systemic shift in how cardiovascular disease prevention is approached in the United States. A more proactive and precise identification of high-risk individuals could result in:
- Reduced Cardiovascular Event Rates: A direct consequence of more effective and timely interventions.
- Lower Healthcare Costs: By preventing costly hospitalizations, emergency room visits, and long-term rehabilitation associated with heart attacks and strokes.
- Improved Quality of Life: For individuals who are spared the debilitating effects of cardiovascular events.
- Enhanced Resource Allocation: Healthcare resources could be more efficiently directed towards those who will benefit most from intensive interventions.
While the study’s findings are compelling, further research and clinical implementation efforts will be necessary to fully realize the potential of apoB testing. This may involve developing more standardized protocols for apoB measurement, educating healthcare providers about its benefits and interpretation, and addressing any remaining cost or accessibility barriers.
The study, titled "Cost-Effectiveness of ApoB, Non-HDL-C, and LDL-C Goals for Primary Prevention Lipid-Lowering Therapy," was supported by the American Heart Association Career Development Award. Coauthors from Northwestern Medicine included Drs. John Wilkins and Samuel Luebbe. Their collective work represents a significant step forward in the ongoing effort to refine cardiovascular risk assessment and improve the lives of millions of Americans. The promise of a more accurate and cost-effective method for identifying individuals at risk for heart disease and stroke offers a hopeful outlook for the future of preventive cardiology.
